


DLOSCEPrep

Free lesson

Chief Complaint Analysis

The first lesson of DLOSCE Prep Course (DLOSCE), free to read.

Chief Complaint Analysis

Topic: 1.1.1

Exam context: DLOSCE entry-level general dentistry clinical reasoning

Difficulty: Foundational

Estimated time: 45–60 minutes

Prereqs: None in this course sequence; upcoming linked topics: Medical History Risk Flags Medication And Allergy Review

Key outputs: You should be able to identify what the patient is actually asking for, separate urgency from preference, extract discriminating symptom details, and choose the safest defensible next step before treatment planning.

What you’ll learn

  • DLOSCE Domain: Patient Assessment and Data Gathering → History triage — Convert a patient’s opening statement into a focused clinical problem list.
  • DLOSCE Domain: Diagnosis and Clinical Reasoning → Differential narrowing — Use pain quality, timing, triggers, and associated findings to separate common dental complaint patterns.
  • DLOSCE Domain: Urgent Care, Infection, Pain, and Safety → Urgency recognition — Identify red-flag complaints that require immediate escalation, same-day care, or deferral of routine treatment.
  • DLOSCE Domain: Treatment Planning and Sequencing → Best-next-step selection — Decide when to gather more history, when to examine, when to stabilize, and when to refer.
  • DLOSCE Domain: Communication, Ethics, and Professionalism → Patient-centered interviewing — Restate and clarify the chief complaint in language that is accurate, respectful, and chart-defensible.

Blueprint mapping

  • Patient Assessment and Data Gathering → Chief complaint elicitation → symptom characterization
  • Diagnosis and Clinical Reasoning → Initial pattern recognition → focused differential generation
  • Urgent Care, Infection, Pain, and Safety → Red-flag screening → escalation threshold recognition
  • Treatment Planning and Sequencing → Best next step → defer vs proceed decisions
  • Communication, Ethics, and Professionalism → Accurate documentation → patient-centered clarification

Why it matters

  • The chief complaint is the first sorting tool in an OSCE station: it tells you whether the task is pain triage, routine care, trauma assessment, infection screening, or communication.
  • Many wrong answers come from treating the patient’s requested procedure instead of the problem hidden inside the complaint.
  • Red-flag wording such as “can’t swallow,” “rapid swelling,” or “woke me from sleep” changes priority faster than radiographs or treatment preferences.
  • Good chief complaint analysis prevents unsafe shortcuts, especially before the later steps of medical history, medication review, and definitive treatment planning.

Key Terms & Must-Know Facts

Key terms

  • Chief complaint (CC): The patient’s main reason for seeking care, ideally in the patient’s own words.
  • History of present illness (HPI): The structured expansion of the complaint using targeted symptom questions.
  • Provoked pain: Pain triggered by stimulus such as cold, heat, biting, or sweets.
  • Spontaneous pain: Pain that occurs without an obvious trigger.
  • Referred pain: Pain perceived away from the true source.
  • Red flag: A history element suggesting emergency risk, spreading infection, airway concern, systemic instability, or non-routine referral threshold.
  • Urgent dental complaint: A problem needing prompt evaluation, often same day, to control pain, infection, or risk.
  • Elective concern: A patient-centered preference or routine need that can wait if safety issues are present.
  • Open-ended question: A question that lets the patient describe the problem without being led.
  • Closed-ended question: A question used to confirm specific features after the initial narrative.
  • Pain chronology: Timing, duration, onset, frequency, and progression of symptoms.
  • Functional impact: Effect on eating, sleeping, speaking, opening, swallowing, or daily activity.
  • Best next step: The safest immediate action based on the complaint and available findings.

Must-know facts

  • Chart the chief complaint in the patient’s own words when possible, then translate it into a clinical question.
  • The complaint is not automatically the diagnosis; “I need a filling” may hide irreversible pulpitis, fracture, or sinus-related pain.
  • Red flags outrank treatment preference.
  • Open first, narrow second: start broad, then ask targeted follow-up questions.
  • On boards, spontaneous, lingering, poorly localized pain usually matters more than cosmetic dissatisfaction.
  • Swelling plus fever, malaise, dysphagia, or trismus raises urgency.
  • Biting pain suggests crack, high occlusion, apical inflammation, or periodontal involvement more than simple reversible sensitivity.
  • Cold sensitivity that resolves immediately points differently from pain that lingers after stimulus removal.
  • The safest answer may be urgent evaluation, deferral, consultation, or emergency referral rather than definitive treatment.
  • Chief complaint analysis is incomplete until you identify the task: diagnose, triage, stabilize, reassure, refer, or proceed with routine care.
Fig 1. Chief complaint triage map
Exam takeaway: Start by deciding whether the complaint signals routine care, urgent dental care, or emergency escalation before choosing any procedure.
flowchart TD
A[Patient opening statement] --> B{Red flag features?}
B -->|Yes| C[Assess airway/systemic risk]
C --> D[Emergency referral or urgent same-day escalation]
B -->|No| E{Pain, swelling, trauma, bleeding, function loss?}
E -->|Yes| F[Focused symptom analysis]
F --> G[Exam and targeted tests]
G --> H[Best next step: stabilize, diagnose, treat, or refer]
E -->|No| I[Routine/elective concern]
I --> J[Comprehensive assessment and sequencing]
Patient interview positioning for dental chief complaint intake
Exam takeaway: Use neutral posture and focused questioning to obtain accurate symptom details without leading the patient.
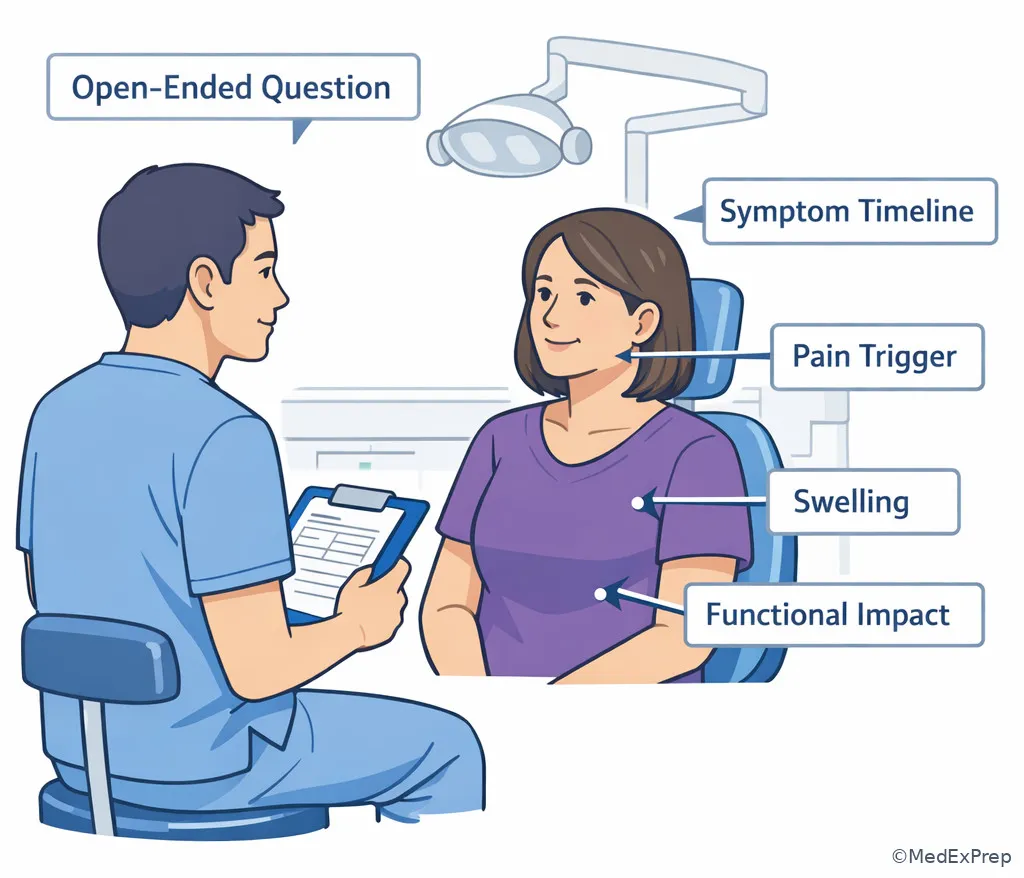
Patient interview positioning for dental chief complaint intake

Core content

1.1.1.1 Define the complaint before you solve it

A. Explanation

The first decision conflict is simple but heavily tested: Do you act on the patient’s requested treatment, or do you first clarify the problem? The correct move is to clarify the problem. A patient saying “I need a crown,” “I want this tooth pulled,” or “my filling fell out” is giving you a starting point, not a final plan. The single rule that resolves the conflict is this: the chief complaint identifies the task; it does not authorize the procedure. In DLOSCE-style reasoning, you must translate the patient’s words into a clinical target: pain source, swelling source, trauma pattern, esthetic concern, functional issue, or preventive request.

Start with an open-ended invitation: “Tell me what brought you in today.” Then narrow the history with focused questions about onset, location, quality, severity, duration, triggers, progression, associated swelling, fever, bad taste, trauma, and impact on chewing or sleep. If the complaint is nonpainful, ask what change the patient noticed, how long it has been present, and whether it bleeds, grows, or interferes with function. This preserves diagnostic neutrality and avoids anchoring too early.

WHY THIS IS TESTED: Boards want to know whether you can avoid premature closure. The testable pattern is a patient request that sounds specific but hides a different clinical problem. See Fig 1.

Key rule: Document the complaint in the patient’s own words, then restate it clinically: “Patient reports lower right tooth pain for 3 days, triggered by cold and chewing, worse at night.” That is far more defensible than charting “needs extraction.”

Memory anchor: Use SOFT-T for the first pass of chief complaint analysis: Site, Onset, Function impact, Trigger, Time course. Add red flags immediately if present.

Complaint clarification flow
Exam takeaway: Convert the patient’s request into a neutral clinical question before you consider treatment.
Hear the patient’s words
Capture the exact reason for visit without correction or interruption.

Request vs problem
If the patient asks for a procedure, translate it into the symptom or concern that needs evaluation.

Expand the history
Ask about timing, trigger, severity, progression, and associated features.

State the task
Decide whether the next step is exam, urgent triage, pain workup, or routine care planning.

B. Worked example

A 43-year-old man presents saying, “I’m here for an extraction on the upper left.” He has obesity and seasonal allergies. He mentions he took ibuprofen before arrival and notes a “sinus headache” last week. He works night shifts and says the tooth “feels loose” when he bites bread. No swelling is visible. The tempting clue is the patient’s direct request for extraction; the distracting detail is the recent sinus pressure.

Reasoning chain: Identify task: not “perform extraction,” but determine why he wants one. Extract key facts: upper left, biting discomfort, possible mobility sensation, recent sinus symptoms, no obvious swelling, self-medicated pain. Apply rule: patient request does not equal indicated treatment. Eliminate distractors: immediate extraction is premature; routine prophylaxis ignores the pain complaint; attributing everything to sinusitis is unsupported without exam. Verify best answer: obtain focused history and perform targeted clinical and radiographic evaluation before deciding treatment.

A board-safe response would be: “I want to understand exactly what that tooth is doing before we decide whether extraction is the right option.” That shows patient-centered communication and defensible sequencing.

C. Exam trap

Common wrong answer: Proceeding directly with the patient’s requested procedure.

Why it is tempting: The patient sounds certain, and the request appears efficient.

Single clue that eliminates it: There has been no focused symptom analysis or diagnostic confirmation; on the exam, skipping assessment is unsafe and indefensible.

D. Checkpoint

Question: A 29-year-old patient says, “My filling came out, so I just need it replaced today.” She has mild asthma and reports that the tooth now hurts only when she drinks cold water, with the pain ending right away. Which is the most appropriate next step?

  1. Replace the restoration immediately — tempting because the patient identifies a lost filling, but wrong because symptom clarification and exam still come first.
  2. Begin antibiotics because cold sensitivity suggests infection — tempting because pain is present, but wrong because isolated brief cold sensitivity does not itself justify antibiotics.
  3. Obtain focused history and examine the tooth before selecting treatment — tempting and correct because the complaint names a possible cause, not the final management decision.
  4. Refer for emergency hospital evaluation — tempting if any pain is overcalled as urgent, but wrong because no airway, systemic, or spreading infection red flags are given.
If you missed this: Review 1.1.1.1 Define the complaint before you solve it — focus on the rule that a requested procedure is not a diagnosis or treatment authorization.

Practitioner Action: Assess the patient’s own words, then clarify onset, trigger, progression, and function. Intervene by reframing the request into a diagnostic task. Refer only if red flags or out-of-scope findings appear. Document the complaint verbatim plus your clinical restatement and immediate triage decision.

1.1.1.2 Extract the discriminating symptom pattern

A. Explanation

The next decision conflict is which symptom detail actually changes your differential and next step? Students often collect many facts but miss the one that matters most. In chief complaint analysis, the highest-yield details are timing, trigger, duration after stimulus, spontaneity, localization, and whether pain is associated with chewing, swelling, or sleep interruption. These details narrow what kind of evaluation you prioritize. For example, brief cold sensitivity points in a different direction from spontaneous throbbing pain that lingers or wakes the patient.

Use a structured symptom grid. Ask: Where is it? When did it start? What triggers it? Does it linger? Can the patient point to one tooth? Is chewing involved? Is there swelling, fever, bad taste, trauma, or recent dental treatment? Can the patient sleep? Did the problem worsen or fluctuate? This pattern-based approach is more useful than asking random questions. It helps you decide whether the complaint sounds like dentin sensitivity, pulpal pain, cracked tooth, occlusal trauma, periodontal tenderness, periapical involvement, or a nonodontogenic mimic requiring broader thinking.

WHY THIS IS TESTED: The exam often gives several true statements, but only one symptom pattern should drive the best next step. The testable pattern is choosing between plausible diagnoses based on a single discriminating clue.

Recall: This is the first topic in the course, so there is no prior topic to build from. As you move into Medical History Risk Flags and Medication And Allergy Review, you will layer systemic and pharmacologic modifiers onto this same symptom framework.

High-Yield Connection: This concept is tested alongside Dental Pain Differentials and Pulpal Diagnosis Terms. Know both the symptom pattern and the appropriate follow-up test on exam day — they are frequently paired in stems.

Symptom pattern sorting flow
Exam takeaway: In pain complaints, the trigger-duration pattern often separates the best next diagnostic direction.
Ask the stimulus
Cold, heat, biting, sweets, spontaneous, or no clear trigger.

Ask what happens after
If pain stops quickly, think differently than if it lingers or occurs spontaneously.

Check localization and function
Well-localized biting pain differs from diffuse night pain or pressure with swelling.

Choose focused exam
Test the most likely source rather than ordering random interventions.

B. Worked example

A 34-year-old woman presents with “tooth pain on the right.” She has controlled hypothyroidism and gastroesophageal reflux disease. She says cold drinks cause pain in a lower molar, but the pain stops within seconds after she swallows. She also mentions occasional jaw clenching at work and points out a new whitening toothpaste. No swelling, fever, or spontaneous pain is reported. The tempting-but-wrong clue is the clenching history, which can push students toward occlusal trauma without enough support.

Reasoning chain: Identify task: characterize the symptom pattern. Extract key facts: cold-triggered, brief, no lingering, no spontaneous pain, no swelling, no sleep disturbance. Apply rule: brief stimulus-provoked pain that ends quickly points away from more advanced pulpal urgency. Eliminate distractors: antibiotics are unsupported; emergency referral is unnecessary; extraction discussion is premature. Verify: focused examination for caries, exposed dentin, defective restoration, or cervical sensitivity is the appropriate next step.

The point is not to make a final endodontic diagnosis from history alone. The point is to choose the right diagnostic lane.

C. Exam trap

Common wrong answer: Equating any temperature sensitivity with severe infection.

Why it is tempting: Candidates overlearn that pain equals pathology requiring urgent treatment.

Single clue that eliminates it: The pain is brief and stimulus-bound rather than lingering or spontaneous.

D. Checkpoint

Question: Which complaint pattern most strongly supports prioritizing a more urgent pulpal/periapical workup over routine sensitivity evaluation?

  1. Cold pain that ends immediately after the drink is removed — tempting because temperature sensitivity is present, but wrong because the nonlingering pattern is less urgent.
  2. Dull pressure after chewing crusty bread one time last week — tempting because biting pain matters, but wrong because isolated mild chewing discomfort is less concerning than spontaneous lingering pain.
  3. Spontaneous night pain that lingers after heat and is hard to localize — tempting and correct because spontaneous, lingering, poorly localized pain raises concern for a more advanced pulpal process needing focused urgent workup.
  4. Sensitivity to sweets around an exposed root surface — tempting because it may be painful, but wrong because this pattern more often fits localized dentin sensitivity.
If you missed this: Review 1.1.1.2 Extract the discriminating symptom pattern — focus on trigger-duration-spontaneity as the key sorting rule.

Practitioner Action: Assess timing, trigger, duration, localization, and function impact for every pain complaint. Intervene with targeted clinical tests guided by the pattern, not by habit. Refer if the pattern suggests nonroutine infection, trauma, or nonodontogenic concern beyond entry-level immediate care. Document the symptom pattern in concise chart language that supports your differential.

Quick Recall:

  • The most useful first distinction in pain history is often provoked vs spontaneous.
  • True or False: A patient request for extraction can be accepted as the final treatment plan before evaluation. False.
  • Name 3 key symptom discriminators: trigger, duration after stimulus, and functional impact.
Fig 2. Pain-history discriminator map
Exam takeaway: Use trigger, lingering, localization, and swelling to narrow the complaint before you choose tests or treatment.
flowchart LR
A[Pain complaint] --> B{Trigger?}
B -->|Cold/sweets| C{Lingering?}
C -->|No| D[Consider superficial sensitivity/caries/exposed dentin]
C -->|Yes| E[Prioritize pulpal evaluation]
B -->|Biting| F[Consider crack/occlusion/apical or periodontal source]
B -->|Spontaneous/night| G[Higher concern for pulpal urgency]
A --> H{Swelling/fever/trismus?}
H -->|Yes| I[Escalate urgency]
H -->|No| J[Continue focused exam]
Labeled pain-pattern comparison in dental anatomy
Exam takeaway: Matching common symptom triggers to likely tooth structures improves early differential narrowing.
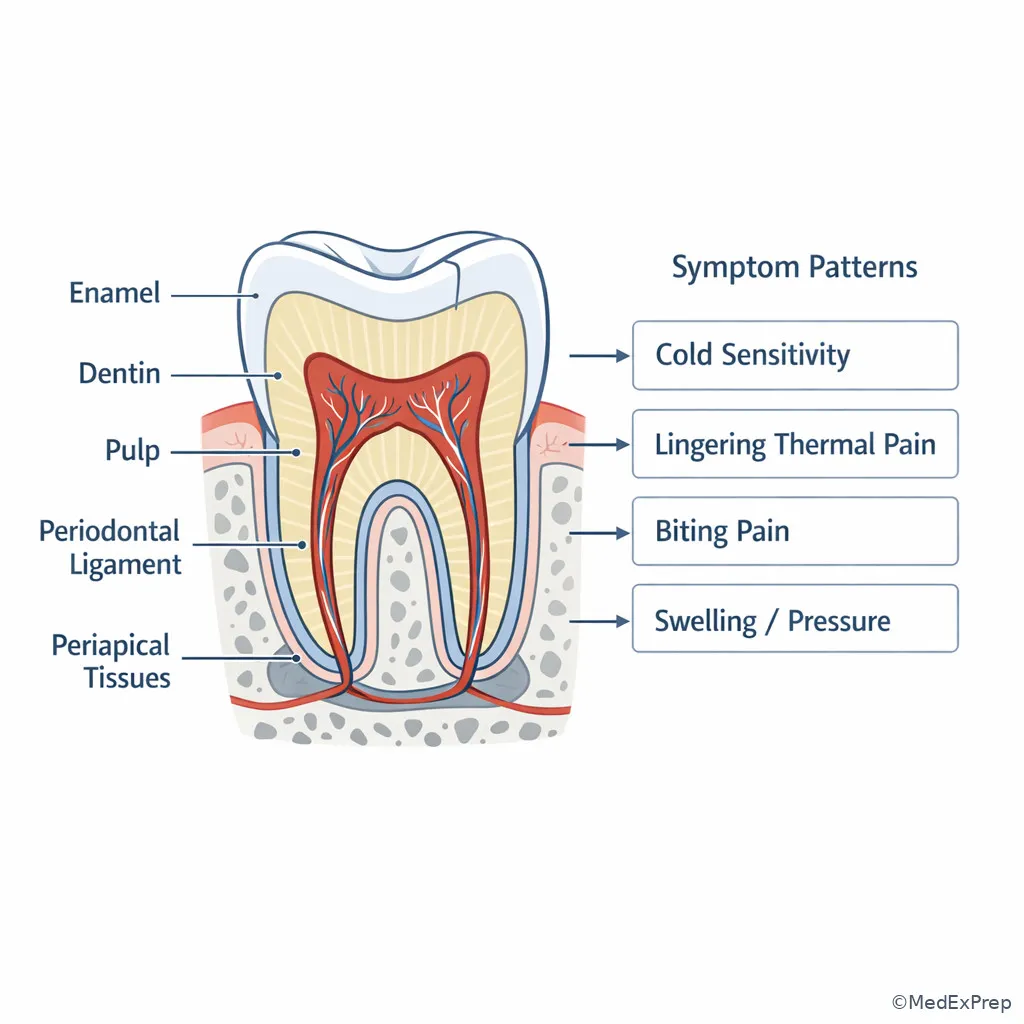
Labeled pain-pattern comparison in dental anatomy

1.1.1.3 Recognize red flags that change urgency

A. Explanation

Now the decision conflict becomes urgent dental issue vs emergency risk vs routine complaint. This is where patient safety dominates. Some complaints can wait for a standard exam; others require same-day urgent dental attention; a smaller group requires emergency referral because the risk is no longer just dental pain. The single rule that resolves the conflict is: if the complaint suggests airway compromise, rapidly spreading infection, significant systemic illness, uncontrolled bleeding, or concerning trauma compromise, escalation outranks definitive office treatment.

Red-flag complaint elements include rapidly increasing swelling, trouble swallowing, trouble breathing, inability to handle secretions, trismus limiting function, fever with facial swelling, malaise with odontogenic symptoms, diffuse rather than localized swelling, postextraction bleeding that does not stop with appropriate pressure, facial trauma with occlusal change or suspected fracture, and severe pain with systemic toxicity. In these situations, an entry-level general dentist candidate should think stabilization, referral, emergency activation when indicated, and clear documentation. You are not expected to manage as the physician or specialist of record.

This section is foundational because many DLOSCE mistakes happen when learners are too procedure-focused. A patient asking for “just antibiotics” or “just something for pain” may actually be describing a red-flag emergency pattern that requires a different level of care.

WHY THIS IS TESTED: The exam wants proof that you will not proceed with routine dentistry when the complaint itself signals danger. See Fig 1 and Fig 3.

Key rule: Swelling plus dysphagia, airway symptoms, rapidly progressive spread, or systemic toxicity is an escalation problem first and a dental procedure problem second.

Memory anchor: Think AIR-SWELL: Airway symptoms, Increasing size, Restricted opening; Swallowing difficulty, Whole-face or diffuse spread, Elevated temperature/ill appearance, Lingering systemic symptoms, Low threshold to escalate.

Urgency escalation flow
Exam takeaway: Red-flag symptoms move the complaint from routine diagnosis to urgent stabilization or emergency referral.
Screen for danger words
Ask about swelling spread, swallowing, breathing, fever, trismus, trauma, and bleeding.

Emergency or urgent?
Airway or systemic compromise requires emergency escalation; localized painful disease may still be urgent same-day care.

Do not overpromise treatment
Stabilize, defer routine care, and arrange appropriate referral or emergency evaluation.

Document clearly
Record the red flags, urgency decision, advice given, and referral pathway.

B. Worked example

A 52-year-old woman presents late in the day saying, “I think I just need antibiotics for a tooth.” She has type 2 diabetes and hypertension. She reports lower right facial swelling that “got a lot bigger today,” difficulty swallowing solid food, and trouble opening fully. She also mentions she had a root canal on another tooth years ago, a distracting clue that does not explain the current urgency. Her temperature in clinic is 100.8°F.

Reasoning chain: Identify task: determine urgency, not choose a routine dental procedure. Extract key facts: rapidly progressive swelling, dysphagia, trismus, fever, systemic risk modifier of diabetes. Apply rule: possible spreading odontogenic infection with deeper space concern requires escalation. Eliminate distractors: routine exam and delayed follow-up are unsafe; simply prescribing medication without escalation ignores airway/systemic risk; definitive specialist-level management is beyond entry-level general dentist scope. Verify best answer: urgent emergency evaluation/referral pathway with appropriate stabilization steps and clear communication.

The correct exam mindset is safety first, scope-aware second, procedure last.

C. Exam trap

Common wrong answer: Managing a potentially spreading infection as a routine localized toothache.

Why it is tempting: The patient frames the visit as “just antibiotics,” and candidates sometimes anchor on a familiar office-level dental pain workflow.

Single clue that eliminates it: Dysphagia or airway-related functional change is a red flag that upgrades urgency immediately.

D. Checkpoint

Question: Which complaint most requires immediate escalation beyond routine same-day dental evaluation?

  1. Cold sensitivity in a premolar that resolves quickly — tempting because pain is present, but wrong because this is not an emergency pattern.
  2. Localized gingival tenderness after popcorn impaction — tempting because it is acute, but wrong because it lacks airway or systemic red flags.
  3. Facial swelling with difficulty swallowing and progressive trismus since morning — tempting and correct because these features suggest a potentially dangerous spreading infection pattern requiring urgent escalation.
  4. Lost temporary crown with mild chewing discomfort — tempting because it may need prompt follow-up, but wrong because it does not carry the same risk threshold.
If you missed this: Review 1.1.1.3 Recognize red flags that change urgency — focus on dysphagia, airway risk, rapid spread, and systemic toxicity as escalation triggers.

Practitioner Action: Assess for swelling spread, swallowing, breathing, fever, and trismus in every infection-related complaint. Intervene by prioritizing stabilization and appropriate urgent disposition. Refer to emergency services or appropriate specialist when findings exceed routine ambulatory general dentistry scope. Document red-flag symptoms, vital signs if available, advice, and referral instructions.

1.1.1.4 Separate urgent symptoms from routine and elective concerns

A. Explanation

Another frequent board conflict is what the patient wants today vs what should actually happen today. A patient may present for whitening, a recall exam, or “just to discuss implants,” but the chief complaint may uncover active pain, swelling, trauma, or bleeding that changes sequence. The reverse also occurs: a patient dramatizes a nonurgent sensitivity complaint, and the candidate unnecessarily over-escalates. The single rule is: sequence care by urgency and risk, not by the loudest preference in the room.

Routine/elective complaints include esthetics, maintenance, replacement of worn restorations without symptoms, denture fit issues without ulceration or inability to function, and stable chronic concerns. Urgent complaints include uncontrolled pain, acute fracture with sharp edges or exposed tissue, new swelling, posttreatment complications, trauma, and bleeding. Mixed visits are especially testable. If the patient says, “I came for cleaning but also this lower tooth kept me up last night,” you must pivot from preventive sequencing to acute problem-focused evaluation.

This is also where communication matters. You can acknowledge the original appointment reason while safely reframing the visit: “We can address your cleaning plan after we evaluate the pain that kept you awake.” That response is patient-centered and clinically defensible.

WHY THIS IS TESTED: The exam often embeds the true urgent issue inside a routine visit reason. See Fig 4.

High-Yield Connection: This concept overlaps with Risk-Based Case Prioritization and Phases Of Care. Exam stems frequently pair a chief complaint with treatment sequencing, so know which problem must be addressed first.

Visit reprioritization flow
Exam takeaway: When routine and acute concerns compete, treat the complaint that changes safety or function first.
List all stated concerns
Include the appointment reason and any newly disclosed pain, swelling, trauma, or bleeding.

Rank by risk and function
If one issue affects safety, sleep, eating, or infection risk, move it ahead of elective care.

Explain the sequence
Tell the patient why the visit focus is changing today.

Set follow-up for deferred items
Address the acute issue now and plan completion of routine care later if appropriate.

B. Worked example

A 26-year-old graduate student presents for “a routine cleaning before my wedding.” She has mild anxiety and iron-deficiency anemia. During intake, she adds that a top front tooth chipped yesterday and now catches on her lip; she also had brief bleeding from the area but no loss of consciousness or facial swelling. She is mainly worried about appearance. The distracting clue is the wedding timeline, which can push the candidate toward cosmetic thinking first.

Reasoning chain: Identify task: re-rank today’s priorities. Extract key facts: recent anterior fracture, soft tissue irritation, minor bleeding, no airway or major trauma red flags, routine cleaning was original purpose. Apply rule: acute structural problem affecting comfort and tissue takes priority over elective prophylaxis. Eliminate distractors: proceeding directly with full routine cleaning ignores the more urgent symptomatic problem; emergency hospital referral is excessive; promising definitive esthetic treatment without evaluation is premature. Verify best answer: focused assessment of the fractured tooth and soft tissue risk first, then determine whether limited smoothing, temporization, or referral is appropriate before elective care.

C. Exam trap

Common wrong answer: Keeping the appointment on the original elective track because that was the scheduled reason for visit.

Why it is tempting: Candidates confuse schedule type with clinical priority.

Single clue that eliminates it: A new acute complaint disclosed during intake changes the task and must be triaged first.

D. Checkpoint

Question: A patient presents for denture adjustment but reports that a lower molar began causing spontaneous pain overnight and now hurts when biting. Which is the most appropriate next step?

  1. Proceed with the denture adjustment only because that was the scheduled procedure — tempting because it respects the appointment type, but wrong because acute pain changes priority.
  2. Shift to focused evaluation of the painful tooth before elective denture care — tempting and correct because symptom-driven reprioritization is the safe sequence.
  3. Dismiss the tooth complaint as stress-related until the denture issue is handled — tempting if the patient has multiple concerns, but wrong because spontaneous overnight pain is clinically meaningful.
  4. Send the patient to the emergency department solely for biting pain — tempting if all acute pain is overtriaged, but wrong because no emergency red flags are described.
If you missed this: Review 1.1.1.4 Separate urgent symptoms from routine and elective concerns — focus on sequencing by risk and function, not appointment label.

Practitioner Action: Assess whether any new complaint changes urgency during intake, even on a routine visit. Intervene by reprioritizing the appointment toward the higher-risk problem. Refer if the newly disclosed issue exceeds office scope or requires specialist/emergency care. Document the original visit reason, the newly revealed complaint, and why the sequence changed.

Quick Recall:

  • True or False: The scheduled procedure always remains the highest priority. False.
  • The best reason to defer elective care is a complaint that changes risk, function, or urgency.
  • Name one routine complaint and one urgent complaint: whitening request; progressive swelling.
Fig 3. Urgency decision tree for dental complaints
Exam takeaway: Red flags and function loss determine whether to reassure, evaluate urgently, or escalate immediately.
flowchart TD
A[Chief complaint] --> B{Airway, dysphagia, rapidly spreading swelling, uncontrolled bleeding, major trauma?}
B -->|Yes| C[Immediate escalation / emergency referral]
B -->|No| D{Severe pain, new swelling, fracture, post-op complication, sleep/eating impact?}
D -->|Yes| E[Same-day urgent dental evaluation]
D -->|No| F{Routine maintenance or elective concern?}
F -->|Yes| G[Routine assessment and scheduling]
F -->|No| H[Focused history and exam to reclassify urgency]
Dental red-flag symptom illustration with face and airway cues
Exam takeaway: Visible spread, swallowing difficulty, and restricted opening are complaint-level clues that upgrade urgency before definitive treatment.
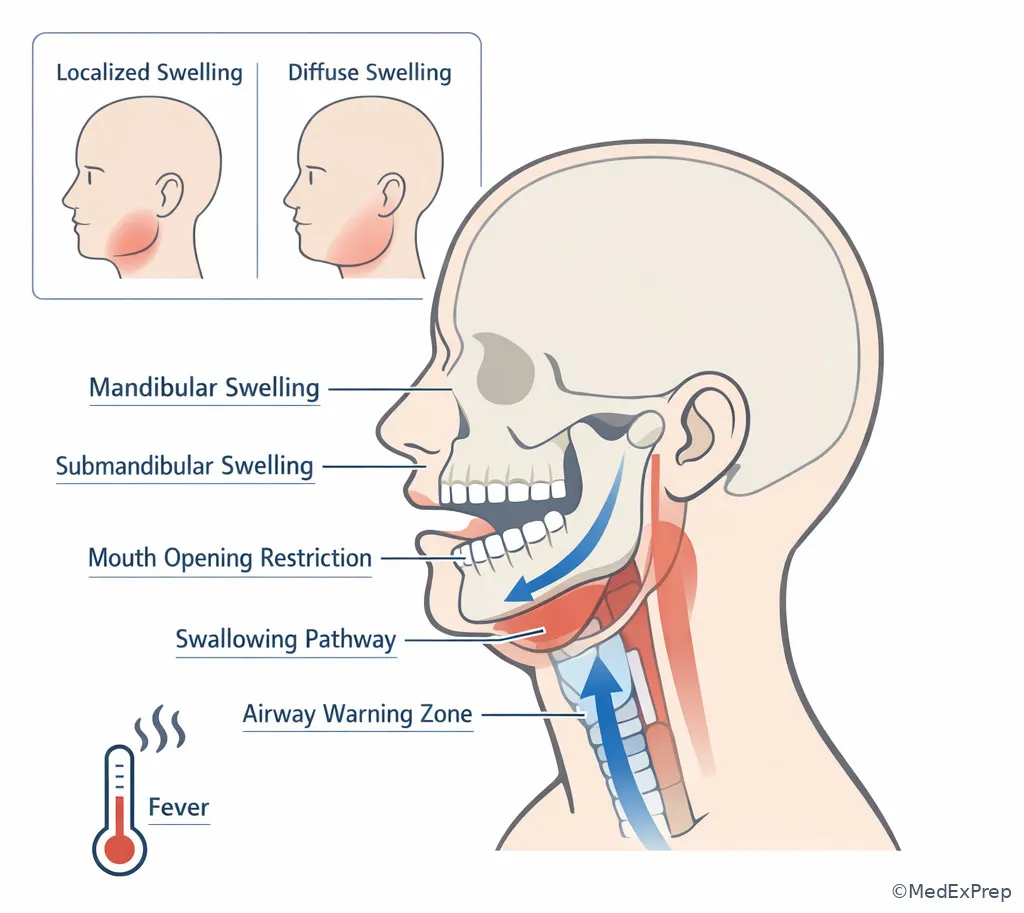
Dental red-flag symptom illustration with face and airway cues

1.1.1.5 Convert the complaint into a defensible next step and chart note

A. Explanation

The last foundational integration task is what do you do after you understand the complaint? The wrong move is to stop at pattern recognition. The correct move is to convert the complaint into a best-next-step statement that is safe, scope-aware, and documentable. The governing rule is: every complaint analysis should end with a triage category, focused plan, and chart-ready summary.

A good chart note links the patient’s words to your clinical interpretation without overstating certainty. Example: “CC: ‘Lower left tooth hurts when I bite.’ HPI: 4 days, localized, worse with chewing, no swelling, no fever, no dysphagia, no spontaneous night pain. Plan: focused exam and diagnostic testing of lower left posterior region today.” This is better than “cracked tooth” before confirmation or “needs extraction” before diagnosis. Your next-step statement should also reflect scope. If the complaint suggests an emergency or specialist threshold, document referral and patient instructions clearly rather than implying definitive specialist treatment will occur in your chair.

Patient communication matters here too. You should explain what you are doing and why: “Based on what you’ve told me, the safest next step is to examine the painful area first and then decide whether this is something we treat today, monitor, or refer.” This is the kind of language that sounds competent in an OSCE.

WHY THIS IS TESTED: Boards assess not just recognition, but action selection and defensible documentation. See Fig 4 and Fig 5.

Recall: In the upcoming topic Medical History Risk Flags, you will add systemic modifiers to this next-step decision. A complaint that seems routine can become delayed or modified once uncontrolled medical disease is identified.

Complaint-to-plan flow
Exam takeaway: Finish every chief complaint interview with a triage label, immediate action, and chartable summary.
State the complaint
Use the patient’s own words first.

Summarize the pattern
Note timing, trigger, red flags, and function impact.

Assign urgency
Routine, urgent same-day, or emergency escalation.

Choose the next step
Focused exam, limited stabilization, defer, consult, or refer.

Document and explain
Record the reasoning and communicate the plan in patient-centered language.

B. Worked example

A 61-year-old man presents saying, “I just want my partial adjusted.” He has osteoarthritis and controlled hyperlipidemia. During intake he reveals that a lower left tooth has had dull pain for 2 weeks, now worse on chewing, with one episode of waking at night; he denies swelling, fever, or difficulty swallowing. He also says he has an old bridge “on that side somewhere,” a tempting clue that may cause anchoring on prosthetic irritation rather than targeted pain evaluation.

Reasoning chain: Identify task: determine best immediate focus and document it. Extract key facts: partial adjustment request, but active posterior tooth pain with chewing and night awakening; no emergency red flags. Apply rule: complaint analysis ends in triage and next step. Eliminate distractors: routine prosthesis adjustment alone ignores the higher-priority pain; emergency referral is unsupported; definitive specialty treatment cannot be chosen before exam. Verify best answer: document the revised chief complaint and perform focused diagnostic assessment of the painful posterior region first, then address the partial if time and safety permit.

A defensible chart line would state both issues but clearly prioritize the painful tooth complaint.

C. Exam trap

Common wrong answer: Writing a vague note such as “patient in pain” and proceeding without a structured plan.

Why it is tempting: Under time pressure, vague documentation feels faster.

Single clue that eliminates it: OSCE scoring rewards explicit reasoning: complaint, symptom pattern, urgency level, and next step must all be visible.

D. Checkpoint

Question: Which charting statement best reflects defensible chief complaint analysis?

  1. “Needs root canal.” — tempting because it sounds decisive, but wrong because it overstates a diagnosis before evaluation.
  2. “Patient reports ‘sharp pain on lower right when chewing for 3 days’; no swelling, fever, or dysphagia; focused exam planned today.” — tempting and correct because it preserves the patient’s report, records key negatives, and states the next step without overcommitting.
  3. “Pain probably from stress.” — tempting when the history seems vague, but wrong because it is unsupported and prematurely dismissive.
  4. “Will extract if confirmed.” — tempting because it sounds conditional, but wrong because it still jumps ahead to a procedural solution rather than documenting the current assessment task.
If you missed this: Review 1.1.1.5 Convert the complaint into a defensible next step and chart note — focus on documenting patient words, key discriminators, urgency, and immediate plan.

Practitioner Action: Assess the complaint until you can state the problem in clinical terms. Intervene by selecting the safest next step within entry-level scope. Refer when the next step is beyond routine ambulatory general dentistry or emergency thresholds are met. Document verbatim complaint, targeted HPI details, red-flag negatives/positives, urgency level, plan, and patient instructions.

Fig 4. Complaint-to-documentation workflow
Exam takeaway: The strongest notes connect the patient’s words to urgency level and a specific next action without overstating diagnosis.
flowchart LR
A[Patient words] --> B[Focused HPI details]
B --> C[Red flag screen]
C --> D[Urgency label]
D --> E[Best next step]
E --> F[Chart note + patient explanation]
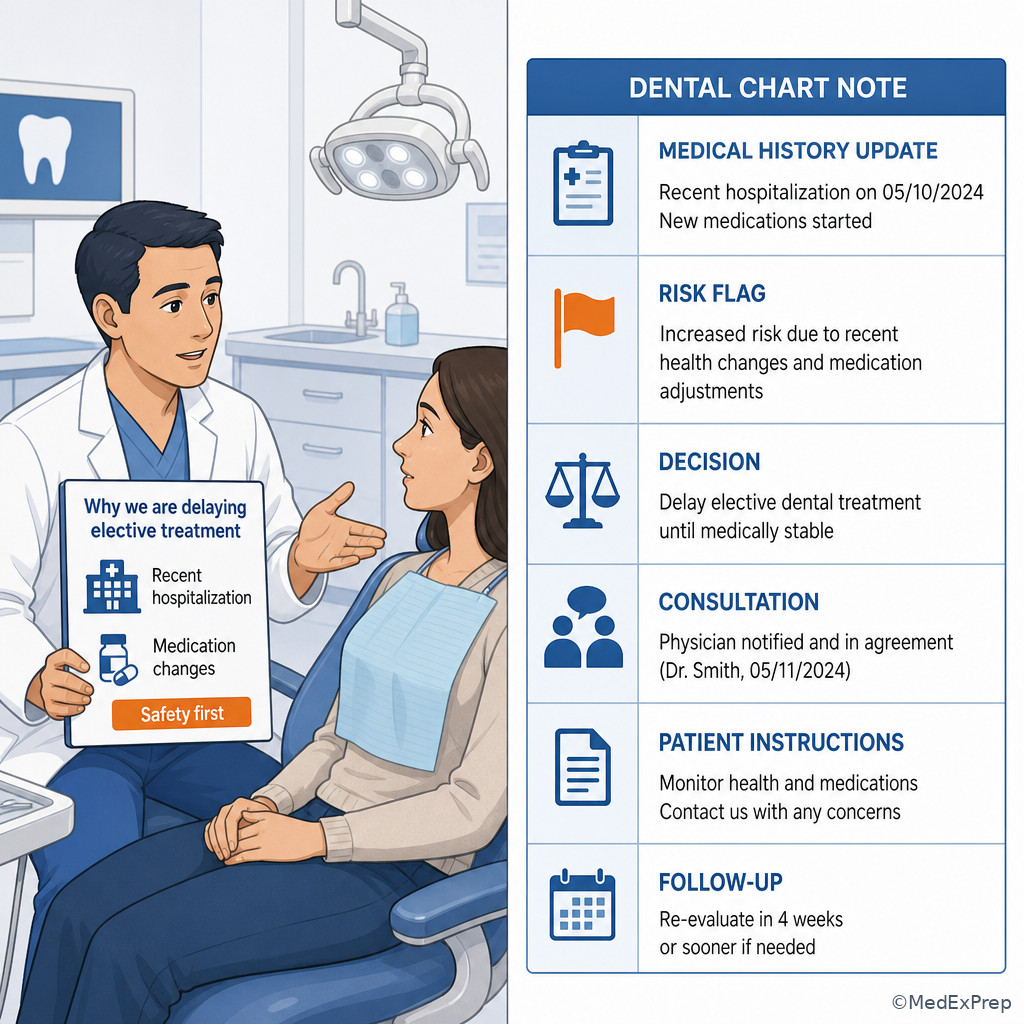
Fig 5. Defensible dental chart note layout for chief complaint analysis
Exam takeaway: A chart note should show patient words, symptom discriminators, urgency findings, and the immediate plan in a clear sequence.

Fig 5. Defensible dental chart note layout for chief complaint analysis
Comparison image of routine visit versus urgent visit sequencing in dentistry
Exam takeaway: Visual sequencing helps distinguish when acute symptoms should displace planned elective care.
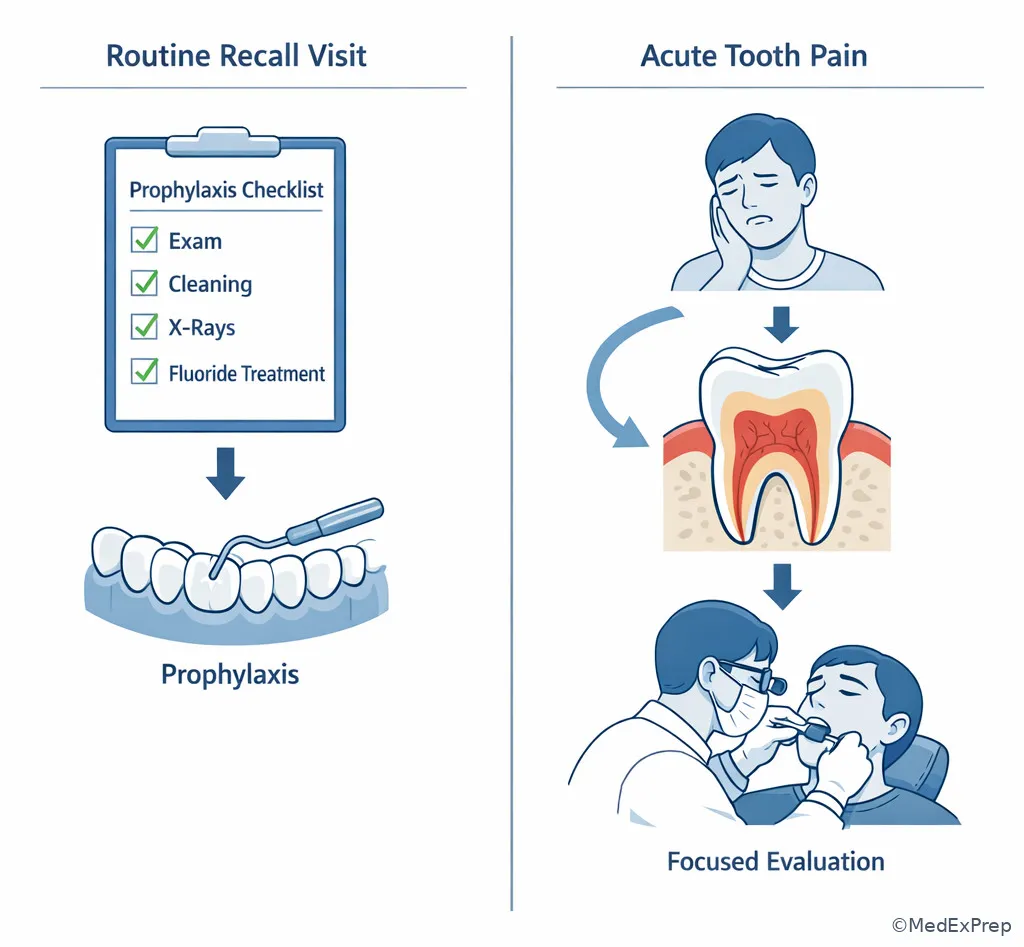
Comparison image of routine visit versus urgent visit sequencing in dentistry
Focused questioning checklist for dental pain intake
Exam takeaway: A short, structured question set captures the symptom details that most often separate similar answer choices.
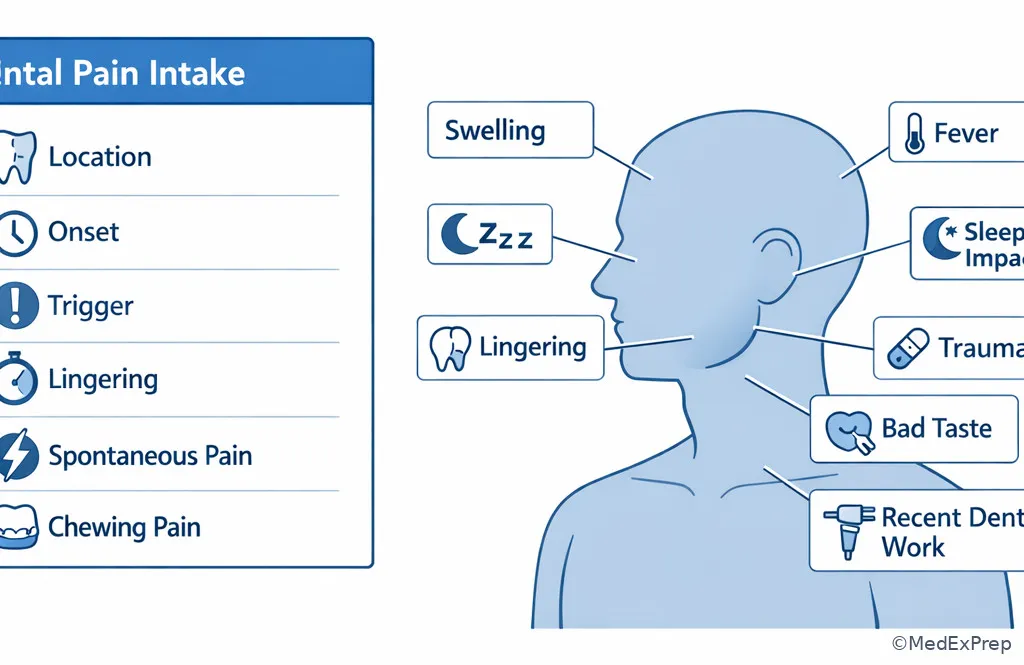
Focused questioning checklist for dental pain intake

Tables

Complaint detail Why it matters What it changes
Patient’s exact words Preserves the presenting concern without clinician bias Improves chart defensibility and communication
Onset and time course Separates sudden acute problems from chronic stable concerns Urgency and likely pathophysiologic lane
Trigger Cold, heat, chewing, sweets, or spontaneous onset narrow possibilities Choice of focused tests and differential
Lingering after stimulus Distinguishes milder superficial sensitivity patterns from more concerning pulpal patterns Urgency of workup
Localization Well-localized versus diffuse symptoms affect source confidence Need for broader differential and targeted exam
Swelling/fever/trismus/dysphagia Complaint-level red flags Urgent escalation threshold
Effect on eating or sleep Signals symptom severity and function loss Same-day prioritization
Recent trauma or dental treatment Changes likely source and possible complications Focused trauma/post-op pathway
Pattern Choose this framing Reject this shortcut Best next step
Patient requests extraction or crown Requested procedure is not the diagnosis Immediate procedural commitment Clarify complaint and examine first
Brief cold sensitivity Trigger-duration pattern matters Assuming severe infection from any thermal pain Focused routine evaluation
Spontaneous night pain with lingering thermal pain More concerning pain behavior Treating as simple sensitivity Prioritize pulpal/periapical workup
Rapid swelling with dysphagia Safety outranks procedure Routine office-only management Immediate escalation/emergency referral
Routine recall plus new acute pain Reprioritize by urgency Staying on elective schedule only Focused acute evaluation first
Vague complaint without clear source Neutral documentation and targeted history Overstated diagnosis in the chart Structured HPI and exam plan
Complaint category Typical clues Common wrong answer Discriminator
Routine/elective Cleaning, whitening, stable prosthesis adjustment, asymptomatic replacement Over-escalating every concern No urgent function loss or red flags
Urgent dental Acute pain, fracture discomfort, new localized swelling, chewing pain, post-op concern Keeping the visit purely elective Symptoms affect comfort/function and need prompt evaluation
Emergency escalation Dysphagia, airway compromise, rapidly spreading swelling, uncontrolled bleeding, major trauma concerns Providing routine definitive office care first Potential systemic or airway threat
Nonodontogenic possibility Poor localization, atypical pattern, mismatch with dental findings Forcing a tooth-based diagnosis too early History pattern does not fit common odontogenic triggers
Patient-request-driven “I need a root canal,” “just pull it,” “just give antibiotics” Accepting the request as treatment plan No diagnosis has been established yet
Charting approach Strong example Weak example
Chief complaint “Patient states, ‘My lower right tooth hurts when I bite.’” “Needs dental work.”
Symptom details 3 days, chewing-triggered, no swelling, no fever, sleep intact “Painful.”
Urgency statement No airway/systemic red flags; urgent focused dental evaluation today No urgency assessment recorded
Plan Focused exam and diagnostic testing before treatment decision “Will fix tooth.”
Referral note Dysphagia and diffuse swelling discussed; patient directed for emergency evaluation “Told patient to go somewhere else.”

Exam Traps & Differentiators

Common traps & distractors: The most common wrong answer is treating the stated request as the true clinical task. This is tempting because patients often sound certain and the request resembles a treatment plan. The discriminator is whether you have enough complaint analysis to justify action. If not, the next step is clarification and targeted evaluation.

Looks similar but isn’t: Acute sensitivity and urgent pulpal pain can both involve thermal triggers, but the discriminator is whether the pain lingers or occurs spontaneously. Routine recall and urgent same-day care can occur in the same visit, but the discriminator is whether the newly disclosed symptom affects safety, function, or urgency.

If the stem says... Think...
“I just need this tooth pulled” Clarify the underlying complaint before accepting the requested procedure
“Cold hurts, but it stops right away” Provoked nonlingering pattern; routine focused evaluation lane
“It woke me up and I can’t tell which tooth” More concerning pulpal pain pattern; urgent diagnostic workup lane
“The swelling got much bigger today and it’s hard to swallow” Emergency escalation threshold
“I came for cleaning, but this tooth started throbbing yesterday” Reprioritize the visit to the acute complaint
“Just give me antibiotics” Do not let the patient select management before triage and diagnosis

Cross-topic confusable pairs: In the upcoming Medical History Risk Flags lesson, some patients with routine-looking complaints will need care modification or deferral because of uncontrolled systemic disease. In Medication And Allergy Review, a patient’s complaint may reflect medication effect, adverse reaction, or mistaken allergy labeling. Here, your job is not to solve those topics yet, but to leave room for them by not anchoring too early.

Review connection: The traps above test complaint reframing, symptom discrimination, and urgency sorting. If any felt unfamiliar, revisit 1.1.1.2 Extract the discriminating symptom pattern and 1.1.1.3 Recognize red flags that change urgency before attempting the Self-check quiz.

Algorithm / Approach

Fig 6. Practical approach to chief complaint analysis
Exam takeaway: A repeatable triage sequence helps you choose the safest defensible next step under OSCE time pressure.
Start with patient words
Ask what brought the patient in today and record the complaint in direct language.

Screen for red flags
If airway, dysphagia, rapidly spreading swelling, uncontrolled bleeding, or major trauma is present, escalate immediately.

Characterize the symptom
Clarify onset, site, trigger, lingering, spontaneity, function impact, and progression.

Assign urgency
Routine, urgent same-day, or emergency referral.

Choose best next step
Focused exam, stabilization, defer elective care, consult, or refer.

Document and explain
State the complaint, discriminators, urgency call, and patient-centered plan.

Rapid Review

  • Requested procedure → not the same as diagnosis
  • Patient quote in chart → stronger than clinician paraphrase alone
  • Provoked brief cold pain → lower urgency than spontaneous lingering pain
  • Night-waking pain → raises concern beyond simple sensitivity
  • Biting pain → think crack/occlusion/apical-periodontal lane before cosmetic explanations
  • Dysphagia with swelling → escalation problem, not routine office care
  • Diffuse swelling → more concerning than localized gingival tenderness
  • Routine visit plus new acute symptom → reprioritize the visit
  • Open-ended first question → reduces anchoring and improves accuracy
  • Function loss → urgency clue even before definitive diagnosis
  • “Just antibiotics” request → patient preference, not management authority
  • Defensible note → patient words + HPI pattern + urgency + next step
  • Emergency referral answer → justified by airway/systemic compromise, not pain alone
  • Best next step → often focused evaluation, not definitive treatment

Memory anchor: For OSCE pacing, use QUOTE → SORT → SCREEN → STEP: quote the patient, sort the symptom pattern, screen red flags, choose the next step.

Self-check quiz

1. A 31-year-old patient says, “I need a crown on this tooth today.” She has mild eczema and seasonal allergies. She adds that the tooth has been sensitive to cold for 1 week, but the pain stops immediately after the drink is removed. Which is the most appropriate next step?

  1. A. Schedule crown preparation immediately
  2. B. Obtain focused history and examine the tooth before selecting treatment
  3. C. Prescribe antibiotics for likely infection
  4. D. Refer to the emergency department

2. A 24-year-old patient presents for whitening consultation. He has mild asthma and no recent dental care. During intake he reports lower molar pain that began with cold drinks and now wakes him at night. Which complaint feature most strongly changes this from a routine esthetic visit to an urgent diagnostic visit?

  1. A. Interest in whitening
  2. B. History of mild asthma
  3. C. Night-waking pain
  4. D. Lack of recent dental care

3. A 47-year-old woman presents saying, “I think food is stuck back there.” She has controlled hypertension and osteoarthritis. She reports localized gingival soreness after popcorn last night, no swelling, no fever, no dysphagia, and she can point to the site exactly. Which is the most appropriate complaint classification?

  1. A. Emergency escalation for spreading infection
  2. B. Urgent same-day localized dental evaluation
  3. C. Purely elective cosmetic concern
  4. D. Immediate hospital management for airway risk

4. A 39-year-old man presents for a denture adjustment. He has GERD and hyperlipidemia. During intake he reports a lower right tooth with sharp pain on chewing for 4 days and one episode of spontaneous pain overnight; no swelling, fever, or trauma. What is the most appropriate next step?

  1. A. Proceed with the denture adjustment only because that was scheduled
  2. B. Shift to focused evaluation of the painful tooth before elective denture care
  3. C. Send him for emergency hospital evaluation because pain was spontaneous once
  4. D. Promise extraction today if the patient wants it

5. A 58-year-old patient says, “Just give me antibiotics.” He has type 2 diabetes and reports facial swelling since yesterday, feverish feeling, and increasing difficulty opening. He denies chest pain. Which single complaint clue most requires escalation of urgency?

  1. A. Request for antibiotics
  2. B. Facial swelling with increasing difficulty opening
  3. C. Type 2 diabetes alone
  4. D. Absence of chest pain

6. A 44-year-old woman presents saying, “My upper left tooth is cracked, so I want it out.” She has anxiety and hypothyroidism. She reports pain only on biting hard foods for 2 weeks, no swelling, no fever, no spontaneous pain, and no sleep interruption. Which is the most defensible immediate response?

  1. A. Agree to extraction because the patient has identified the cause
  2. B. Explain that the complaint needs focused evaluation before any treatment decision
  3. C. Prescribe antibiotics because chewing pain suggests apical infection
  4. D. Refer to the emergency department for all cracked-tooth complaints

7. A 63-year-old man presents for routine prophylaxis. He has controlled atrial fibrillation and chronic kidney disease stage 3. On questioning, he reports that a lower posterior tooth developed spontaneous throbbing pain last night and now feels “high” when he bites; he also notes mild localized swelling near the tooth but no dysphagia, no breathing difficulty, and no diffuse facial swelling. Which is the most appropriate next step?

  1. A. Continue with prophylaxis because the scheduled visit is routine
  2. B. Reclassify the visit as urgent same-day dental evaluation of the painful tooth
  3. C. Send him directly to emergency services because any swelling requires hospital care
  4. D. Chart “likely abscess, extraction needed” before examination

8. A 36-year-old patient says, “I chipped a front tooth, but I mostly just want my cleaning.” She has iron-deficiency anemia and controlled asthma. The chip occurred today, the edge is sharp and catching her lip, there is no loss of consciousness, no malocclusion, and no facial swelling. Which is the most appropriate sequencing decision?

  1. A. Perform the full cleaning first, then discuss the chip if time remains
  2. B. Focus first on evaluation and limited management of the acute chipped tooth issue
  3. C. Refer immediately to emergency services because all dental trauma is emergent
  4. D. Ignore the chip because the patient says the cleaning matters more

Answer key

1. Answer: B

A. Schedule crown preparation immediately — Tempting because the patient requests a crown and there is localized sensitivity. Incorrect for this scenario because a requested procedure is not yet the indicated treatment; the single discriminating clue is that no focused evaluation has been completed. Authoritative dental diagnostic standards require assessment before definitive treatment selection. Sources: ADA oral health topics; Stefanac and Nesbit.

B. Obtain focused history and examine the tooth before selecting treatment — Tempting because it may feel less decisive, but it is correct. The brief cold sensitivity pattern and patient-request framing both support diagnostic clarification first; the discriminating clue is symptom analysis before procedure choice. Sources: Stefanac and Nesbit; CDT principles of diagnosis and treatment planning.

C. Prescribe antibiotics for likely infection — Tempting because pain can make infection seem likely. Incorrect because isolated brief cold sensitivity without swelling or systemic signs does not justify empiric antibiotic management; the discriminating clue is the absence of infection red flags. Sources: ADA guideline principles on antibiotic stewardship in dental pain/swelling contexts.

D. Refer to the emergency department — Tempting if any dental pain is overtriaged. Incorrect because there are no airway, systemic, or major trauma findings; the discriminating clue is a stable symptom pattern without red flags. Sources: ADA and standard urgent care triage principles.

If you missed this: Review 1.1.1.1 Define the complaint before you solve it — focus on the rule that the patient’s requested procedure does not determine the treatment plan.

2. Answer: C

A. Interest in whitening — Tempting because it explains why the patient came in. Incorrect because appointment reason does not determine urgency; the discriminating clue is that a new pain history supersedes the elective request. Sources: Stefanac and Nesbit.

B. History of mild asthma — Tempting because medical history matters in later sequencing. Incorrect here because asthma does not itself explain the urgency shift; the discriminating clue is symptom behavior, not the comorbidity. Sources: entry-level dental assessment standards.

C. Night-waking pain — Correct because it is a high-yield symptom discriminator suggesting a more urgent pain pattern than routine sensitivity alone. The single clue is pain that wakes the patient from sleep, which changes priority. Sources: pulpal pain history principles in standard endodontic diagnosis texts and dental diagnosis references.

D. Lack of recent dental care — Tempting because overdue care can increase disease burden. Incorrect because it does not by itself establish urgency; the discriminating clue remains the night pain. Sources: standard dental diagnostic reasoning texts.

If you missed this: Review 1.1.1.2 Extract the discriminating symptom pattern — focus on spontaneous or night pain as a stronger urgency clue than routine visit type.

3. Answer: B

A. Emergency escalation for spreading infection — Tempting because the problem is acute and oral soreness can be mistaken for infection. Incorrect because the symptoms are localized and lack systemic or airway red flags; the discriminating clue is exact localization without fever, dysphagia, or diffuse swelling. Sources: ADA urgent care principles; dental diagnosis texts.

B. Urgent same-day localized dental evaluation — Correct because a new symptomatic localized problem merits focused prompt evaluation, even if it is not an emergency. The single clue is acute localized soreness after food impaction with no emergency features. Sources: Stefanac and Nesbit.

C. Purely elective cosmetic concern — Tempting if the soreness seems minor. Incorrect because the patient has an active symptom requiring assessment; the discriminating clue is that this is a current painful complaint, not a preference-based visit. Sources: treatment planning fundamentals.

D. Immediate hospital management for airway risk — Tempting if candidates overreact to any oral pain. Incorrect because airway risk signs are absent; the discriminating clue is no swelling, fever, or dysphagia. Sources: standard dental emergency triage guidance.

If you missed this: Review 1.1.1.3 Recognize red flags that change urgency — focus on the difference between localized acute dental issues and true emergency escalation signs.

4. Answer: B

A. Proceed with the denture adjustment only because that was scheduled — Tempting because it respects the appointment plan. Incorrect because the new complaint changes clinical priority; the discriminating clue is chewing pain plus spontaneous overnight pain. Sources: treatment sequencing principles in dental care planning.

B. Shift to focused evaluation of the painful tooth before elective denture care — Correct because symptoms suggesting acute tooth pathology should be addressed before elective prosthetic adjustments. The single clue is that an acute painful complaint was disclosed during intake. Sources: CDT and entry-level treatment planning standards.

C. Send him for emergency hospital evaluation because pain was spontaneous once — Tempting because spontaneous pain feels serious. Incorrect because emergency escalation requires more than a single spontaneous episode without airway/systemic compromise; the discriminating clue is absence of swelling, fever, or dysphagia. Sources: ADA urgent care triage principles.

D. Promise extraction today if the patient wants it — Tempting as a decisive pain solution. Incorrect because procedure choice follows diagnosis, not the patient’s anticipated preference; the discriminating clue is no diagnostic confirmation. Sources: Stefanac and Nesbit.

If you missed this: Review 1.1.1.4 Separate urgent symptoms from routine and elective concerns — focus on reprioritizing a scheduled elective visit when acute pain is disclosed.

5. Answer: B

A. Request for antibiotics — Tempting because it sounds like the patient believes infection is present. Incorrect because patient preference does not determine urgency; the discriminating clue is objective complaint severity, not the requested therapy. Sources: ADA antibiotic stewardship principles.

B. Facial swelling with increasing difficulty opening — Correct because progressive swelling with trismus is a red-flag pattern that can indicate spreading infection requiring escalation. The single clue is increasing difficulty opening. Sources: ADA emergency/urgent care principles; standard oral infection triage guidance.

C. Type 2 diabetes alone — Tempting because diabetes can worsen infection risk. Incorrect because diabetes is an important modifier but not the single complaint feature that most directly determines immediate escalation here; the discriminating clue remains progressive swelling/trismus. Sources: dental management of medically complex patients texts.

D. Absence of chest pain — Tempting because chest pain is a major medical symptom generally. Incorrect because it does not help classify odontogenic urgency here; the discriminating clue is infection-related functional change, not absence of unrelated symptoms. Sources: general dental urgent triage standards.

If you missed this: Review 1.1.1.3 Recognize red flags that change urgency — focus on progressive swelling and trismus as escalation clues.

6. Answer: B

A. Agree to extraction because the patient has identified the cause — Tempting because the history of biting pain on hard foods can suggest crack-related disease. Incorrect because even a plausible self-diagnosis still requires evaluation before treatment commitment; the discriminating clue is that the patient request is not yet a confirmed management decision. Sources: Stefanac and Nesbit; treatment planning standards.

B. Explain that the complaint needs focused evaluation before any treatment decision — Correct because the symptom pattern suggests a diagnostic lane, not a definitive procedure. The single clue is pain only on biting hard foods without infection red flags, which supports targeted assessment first. Sources: standard dental diagnosis and treatment planning references.

C. Prescribe antibiotics because chewing pain suggests apical infection — Tempting because chewing pain can occur with apical involvement. Incorrect because there is no swelling, fever, or systemic evidence supporting empiric antibiotic use; the discriminating clue is isolated biting pain without red-flag infectious signs. Sources: ADA antibiotic guidance.

D. Refer to the emergency department for all cracked-tooth complaints — Tempting if trauma or fracture is generalized into emergency care. Incorrect because this stable complaint lacks emergency features; the discriminating clue is no swelling, fever, or sleep disruption. Sources: standard dental urgent care principles.

If you missed this: Review 1.1.1.1 Define the complaint before you solve it — focus on rejecting patient-request-driven procedural shortcuts.

7. Answer: B

A. Continue with prophylaxis because the scheduled visit is routine — Tempting because the patient came for maintenance and appears medically stable overall. Incorrect because the new complaint includes spontaneous throbbing pain, biting change, and localized swelling, which require reprioritization; the discriminating clue is active acute symptom burden. Sources: treatment sequencing standards.

B. Reclassify the visit as urgent same-day dental evaluation of the painful tooth — Correct because there is an acute dental complaint without current emergency airway features. The single clue is localized swelling with spontaneous pain but no dysphagia or diffuse facial spread, placing this in urgent same-day rather than emergency escalation. Sources: ADA urgent dental care principles; Stefanac and Nesbit.

C. Send him directly to emergency services because any swelling requires hospital care — Tempting because swelling raises concern. Incorrect because not all swelling is emergent; the discriminating clue is the absence of airway compromise, dysphagia, or diffuse rapidly spreading swelling. Sources: dental emergency triage guidance.

D. Chart “likely abscess, extraction needed” before examination — Tempting because the symptom cluster may suggest infection. Incorrect because documentation should record the complaint and plan without overstating diagnosis or treatment; the discriminating clue is that examination is still pending. Sources: objective charting and diagnosis principles.

If you missed this: Review 1.1.1.4 Separate urgent symptoms from routine and elective concerns — focus on reclassifying a routine visit when acute pain and localized swelling are disclosed.

8. Answer: B

A. Perform the full cleaning first, then discuss the chip if time remains — Tempting because the patient says the cleaning is the main goal. Incorrect because an acute fractured edge injuring soft tissue changes priority; the discriminating clue is same-day sharp edge catching the lip. Sources: dental trauma and sequencing fundamentals.

B. Focus first on evaluation and limited management of the acute chipped tooth issue — Correct because the complaint has become an acute symptomatic problem even without major trauma red flags. The single clue is soft tissue-catching sharpness from today’s fracture, which should be addressed before elective prophylaxis. Sources: standard entry-level dental trauma assessment and treatment planning principles.

C. Refer immediately to emergency services because all dental trauma is emergent — Tempting because trauma language sounds serious. Incorrect because there is no loss of consciousness, malocclusion, facial swelling, or other emergency-level red flag; the discriminating clue is isolated uncomplicated acute tooth injury. Sources: dental trauma triage standards.

D. Ignore the chip because the patient says the cleaning matters more — Tempting as a patient-autonomy misinterpretation. Incorrect because patient preference does not override safe sequencing when an acute symptomatic issue is present; the discriminating clue is active soft tissue irritation. Sources: patient-centered care and clinical prioritization standards.
If you missed this: Review 1.1.1.4 Separate urgent symptoms from routine and elective concerns — focus on sequencing acute symptomatic issues ahead of elective care even when the patient prioritizes the routine visit.

References

  • Stefanac, Stephen J., and Samuel P. Nesbit. Diagnosis and Treatment Planning in Dentistry. 4th ed., Elsevier, 2024.
  • American Dental Association. “Antibiotic Stewardship.” ADA, official clinical resources.
  • Little, James W., et al. Dental Management of the Medically Compromised Patient. 10th ed., Elsevier, 2024.
  • Hupp, James R., et al. Contemporary Oral and Maxillofacial Surgery. 8th ed., Elsevier, 2023.
  • Andreasen, Jens O., et al. Textbook and Color Atlas of Traumatic Injuries to the Teeth. 5th ed., Wiley Blackwell, 2018.

Last reviewed: March 15, 2026

Lesson 2

Medical History Risk Flags

Medical History Risk Flags

Topic: 1.1.2

Course: DLOSCE Prep Course (DLOSCE)

Audience: Entry-level general dentist candidates preparing for the JCNDE DLOSCE

What you’ll learn

  • DLOSCE Domain: Patient Assessment and Data Gathering → History triage — identify medical history findings that change routine dental care.
  • DLOSCE Domain: Medical Risk, Pharmacology, and Patient Management → Contraindication checking — distinguish stable chronic disease from unstable disease that may require deferral or consultation.
  • DLOSCE Domain: Treatment Planning and Sequencing → Best-next-step selection — decide when to proceed, modify, delay, or refer.
  • DLOSCE Domain: Urgent Care, Infection, Pain, and Safety → Escalation thresholds — recognize when recent hospitalization, infection, or medication change signals increased risk.
  • DLOSCE Domain: Communication, Ethics, and Professionalism → Documentation and patient-centered explanation — communicate why additional information or medical consultation is needed before care.

Blueprint mapping

  • DLOSCE Domain: Patient Assessment and Data Gathering → medical history screening
  • DLOSCE Domain: Medical Risk, Pharmacology, and Patient Management → unstable disease recognition
  • DLOSCE Domain: Treatment Planning and Sequencing → defer versus modify elective treatment
  • DLOSCE Domain: Communication, Ethics, and Professionalism → explain delay/consultation rationale

Estimated time: 45–60 minutes

Prereqs: Chief Complaint Analysis

Key outputs: You should be able to identify red-flag medical history items, decide whether dental care can proceed today, determine when a medical consult is needed, and document a defensible risk-based plan.

Why it matters

  • A common DLOSCE error is focusing on the tooth and missing the patient’s systemic risk.
  • Many stems test whether you will delay elective care rather than push ahead with an otherwise straightforward dental procedure.
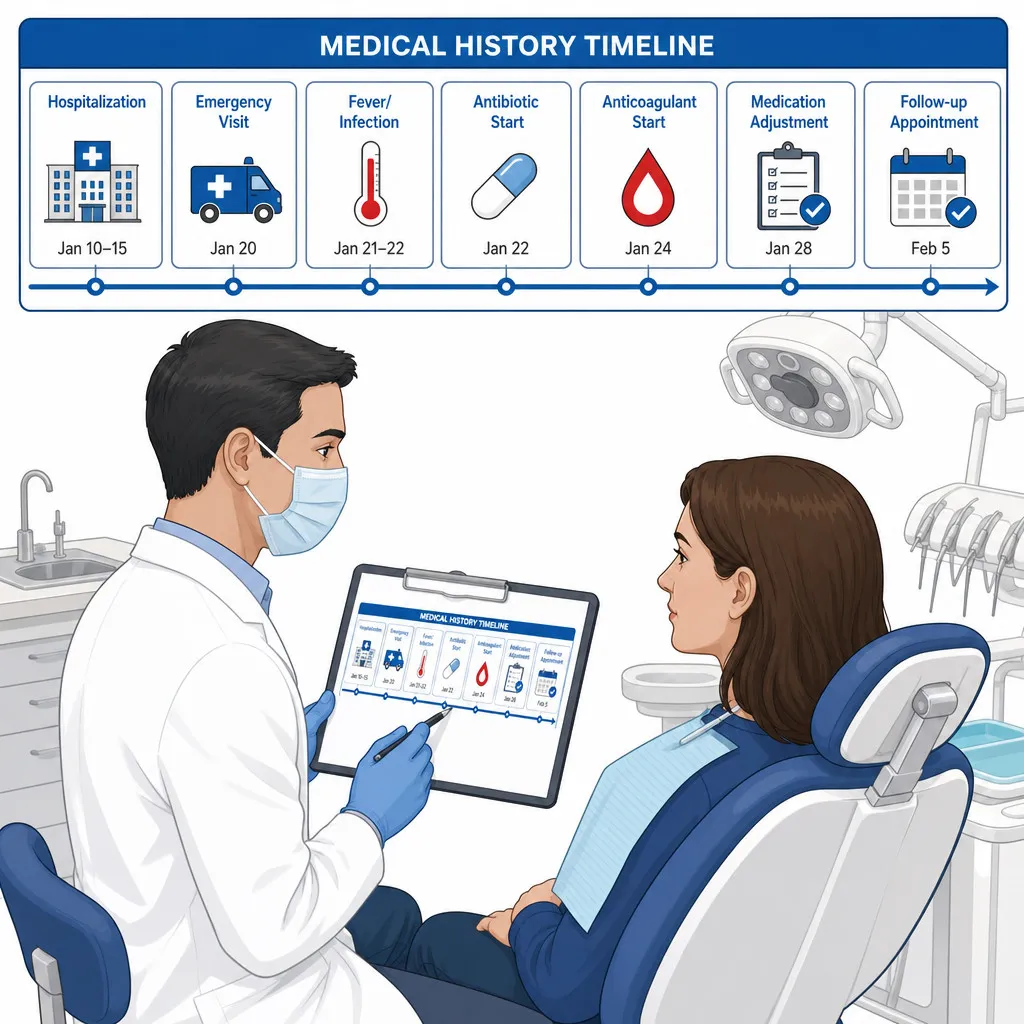
  • Medical history risk flags often appear indirectly: recent hospitalization, “new meds,” poorly controlled symptoms, or vague statements like “my doctor is still adjusting things.”
  • The safest answer is often not a procedure; it is a clarification, consultation, or deferral.

Key Terms & Must-Know Facts

Key terms

  • Risk flag: a history element that may change timing, setting, or modification of dental care.
  • Elective care: nonurgent treatment that can be postponed without significant harm.
  • Urgent care: treatment needed soon for pain, infection, or function, but not immediate life-threatening instability.
  • Medical consultation: communication with the patient’s physician or relevant provider to clarify status or treatment implications.
  • Unstable disease: active symptoms, recent decompensation, medication changes, or recent hospitalization indicating poor control.
  • Recent hospitalization: clue to incomplete recovery, medication changes, or unresolved instability.
  • Bleeding risk: elevated chance of excessive bleeding from disease or anticoagulant/antiplatelet therapy.
  • Infective burden: active infection or immunocompromised state that may alter timing or need for escalation.
  • Functional status: how well a patient tolerates exertion; helps reveal hidden cardiopulmonary instability.
  • Glycemic instability: poor diabetes control, frequent hypoglycemia, or symptomatic hyperglycemia affecting treatment safety.
  • Airway concern: history or symptoms suggesting breathing compromise, especially with facial swelling or severe respiratory disease.
  • Scope-aware referral: recognizing when the safest next step is physician consult, specialist referral, or emergency evaluation.

Must-know facts

  • Stable chronic disease does not automatically prohibit routine dental care.
  • Unstable symptoms matter more than the diagnosis label alone.
  • Recent hospitalization, recent infection, and recent medication changes are classic exam clues that more clarification is needed.
  • Elective treatment is commonly delayed for uncontrolled cardiovascular, endocrine, respiratory, renal, hepatic, or bleeding disorders.
  • A patient who says “my doctor is still adjusting my medications” should trigger follow-up questions before treatment.
  • When the stem includes chest pain, shortness of breath at rest, uncontrolled bleeding, altered mental status, or spreading infection, prioritize urgent escalation over routine dentistry.
  • For DLOSCE reasoning, the key question is often: Can I safely proceed today in entry-level outpatient dental practice?
  • Documentation should include the finding, why it matters, the action taken, and the patient communication provided.
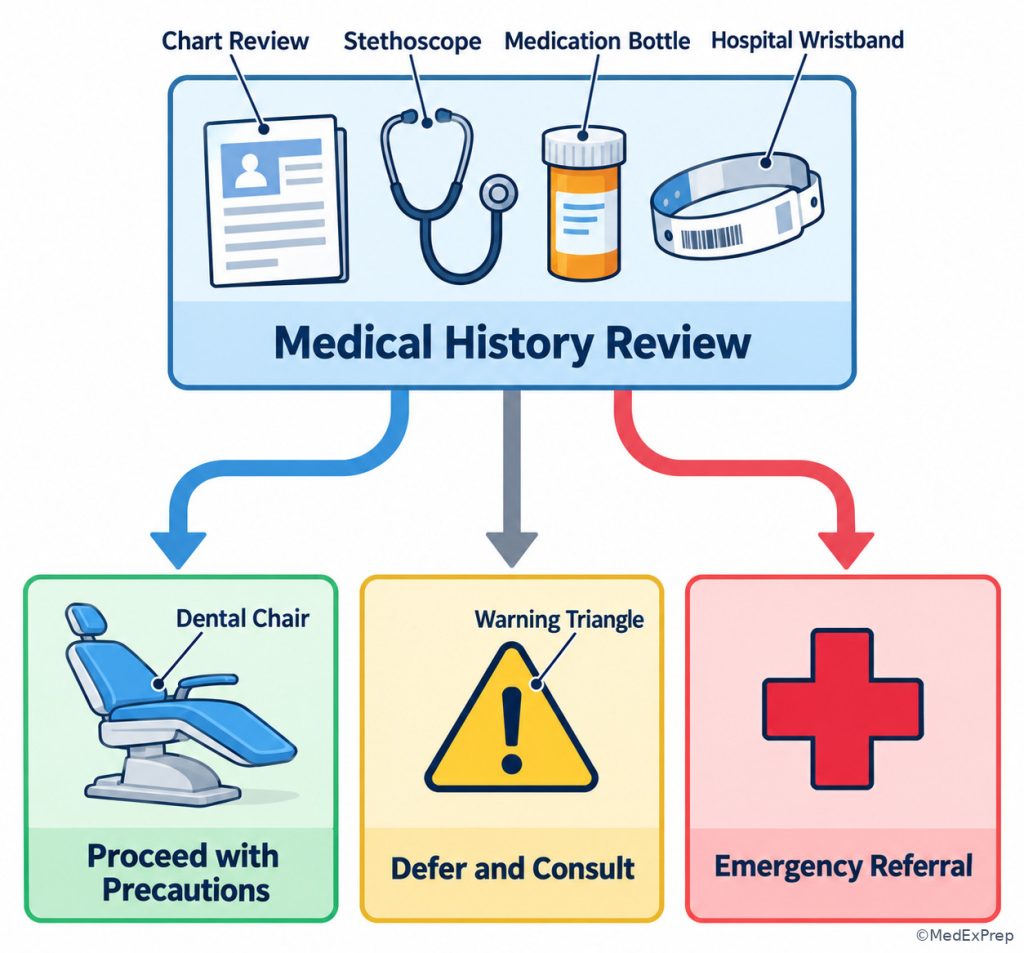
Fig 1. Medical history triage framework
Exam takeaway: Use a stability-first screen to decide whether to proceed, modify care, obtain consultation, or defer treatment.
flowchart TD
A[Medical history finding] --> B{Active symptoms or recent decompensation?}
B -- Yes --> C[Delay elective care]
C --> D{Emergency features?}
D -- Yes --> E[Urgent referral or EMS]
D -- No --> F[Medical consult and treatment modification]
B -- No --> G{Condition controlled and understood?}
G -- Yes --> H[Proceed with appropriate precautions]
G -- No --> I[Clarify history, meds, and recent changes before treatment]

See Fig 1 for the core stability-first framework that should organize your thinking before you look at the dental procedure itself.

History clue Why it matters Typical safest next step
Recent hospitalization May signal recent instability or medication changes Clarify diagnosis, date, current status, and discharge instructions
Chest pain, dyspnea, syncope Possible unstable cardiovascular or respiratory disease Defer elective care; assess urgency; refer appropriately
Frequent hypoglycemia or uncontrolled diabetes Higher risk during appointments and poorer healing Modify timing, confirm control, consider consultation
New anticoagulant or bleeding disorder Procedure-related bleeding implications Review indication, drug, timing, and planned invasiveness
Kidney or liver disease Drug handling, bleeding, infection, and overall tolerance may change Modify plan and clarify severity/current status
Recent infection or fever Possible systemic stress or unresolved illness Determine source, current symptoms, and whether to postpone

Core content

1.1.2.1 Foundational screen: stable chronic disease versus unstable disease

A. Explanation

The first decision conflict is choose routine progression versus reject same-day elective care. Students often overreact to disease labels and underreact to instability clues. The discriminating rule is simple: stable, controlled, familiar disease may allow routine care with modifications; unstable, symptomatic, recently changed, or recently hospitalized disease should slow you down or stop you. In board-style stems, the single finding that resolves the conflict is often not the diagnosis itself but a signal of poor control: exertional chest pain, shortness of breath at rest, frequent hypoglycemia, recent admission, new anticoagulant start, dialysis yesterday with fatigue, or “my doctor is changing my doses because things have been off.”

WHY THIS IS TESTED: exam writers want to know whether you can separate a patient with a chronic condition from a patient who is medically unstable today. The wrong answer is often an otherwise reasonable dental treatment offered at the wrong time.

Use three quick questions: Is the disease active or symptomatic now? Has anything major changed recently? Does the planned dental care increase the specific risk tied to that condition? This topic builds directly on chief complaint triage: in the prior lesson, the question was what the patient wants treated; here, the question is whether the patient is safe for treatment at all.

Concept flow: Stability screen
Identify condition
Name the medical problem and planned dental procedure.

Check stability
Ask about active symptoms, recent hospitalization, and recent medication changes.

Match risk to procedure
Decide whether routine, invasive, or urgent dental care changes the risk.

Act safely
Proceed, modify, consult, defer, or escalate.

Recall: In Chief Complaint Analysis, we covered urgency clues such as swelling, bleeding, trauma, and pain timing. Here, we build on that by asking whether the medical background changes what can be done safely today even when the dental complaint seems routine.
Memory anchor: Think SAFE before treatment: Symptoms now, Admission/recent illness, Fresh medication changes, Elective versus urgent procedure. If any letter is concerning, pause and reassess.

B. Worked example

A 62-year-old man presents for crown preparation on a fractured mandibular molar. He has hypertension, coronary artery disease, and type 2 diabetes. He casually reports that he was “in the hospital last week for some heart thing,” now feels tired climbing stairs, and says his cardiologist added a new medication yesterday. He also mentions mild tooth sensitivity to cold and brings a normal-looking home glucose log from two months ago. The task is the most appropriate next step.

Reasoning chain: Identify task: decide whether elective restorative care should proceed. Extract key facts: recent hospitalization, exertional limitation, new cardiovascular medication, multiple comorbidities. Apply rule: recent cardiac instability and medication adjustment outweigh the routine dental need. Eliminate distractors: proceeding with local anesthesia and monitoring is tempting because the chief complaint is minor and the patient is seated comfortably now; however, this is still elective care in a patient with recent unresolved cardiovascular change. Giving only brief stress-reduction instructions without clarifying status misses the key risk flag. Verify: safest answer is to defer elective treatment and obtain medical clarification regarding diagnosis, current stability, and any precautions before rescheduling.

C. Exam trap

Common wrong answer: Proceed with the appointment because the patient is not reporting chest pain in the chair. Why it is tempting: candidates focus on the immediate absence of symptoms and the routine nature of the planned procedure. Single clue that eliminates it: recent hospitalization with a new cardiovascular medication means disease status is not yet clearly stable.

D. Checkpoint

Question: A 58-year-old woman presents for elective scaling and root planing. She has chronic kidney disease, hypertension, and rheumatoid arthritis. She says, “I was admitted three days ago for fluid overload, but I feel mostly fine now,” and her nephrologist changed two medications yesterday. Which is the most appropriate next step?

  1. Proceed with treatment because periodontal disease is chronic and delaying worsens inflammation.
  2. Obtain clarification of current medical status and defer elective care pending stability assessment.
  3. Administer routine local anesthesia and shorten the visit to reduce stress.
  4. Refer immediately to oral surgery for hospital-based periodontal therapy.

Answer: B

  • A: Tempting because active periodontal disease does need treatment; wrong because recent hospitalization and medication changes create unresolved medical risk.
  • B: Correct because the issue is not the periodontal diagnosis but unclear stability after recent decompensation.
  • C: Tempting because stress reduction is often helpful; wrong because modification does not replace clarification when disease may still be unstable.
  • D: Tempting because the patient seems medically complex; wrong because specialty transfer is not the immediate issue—medical clarification is.
If you missed this: Review 1.1.2.1 Foundational screen: stable chronic disease versus unstable disease — focus on the discriminating rule that recent hospitalization or fresh medication changes can make elective care inappropriate even when the patient looks comfortable.
Practitioner Action: ASSESS active symptoms, recent hospitalization, and medication changes; INTERVENE by deferring elective care when stability is unclear; REFER to the physician or appropriate medical provider for clarification, or to emergency care if symptoms suggest acute instability; DOCUMENT the medical red flags, the reason for deferral, patient instructions, and planned follow-up.

1.1.2.2 System-by-system red flags: what changes care and what does not

A. Explanation

The next decision conflict is choose meaningful red flags versus reject irrelevant history noise. DLOSCE stems frequently include long histories to test whether you can identify the one system finding that truly drives management. A well-controlled patient with a past diagnosis but no symptoms and no recent changes may proceed with routine modifications. A patient with current cardiovascular symptoms, brittle diabetes, active respiratory limitation, dialysis-related issues, liver disease with bleeding signs, or a known bleeding disorder needs a more cautious plan. Do not memorize disease lists in isolation; connect each system to the practical chairside concern:

  • Cardiovascular: ischemia, arrhythmia symptoms, recent hospitalization, exertional intolerance, anticoagulation context.
  • Endocrine: glycemic instability, missed meals, steroid use, adrenal concerns in selected settings.
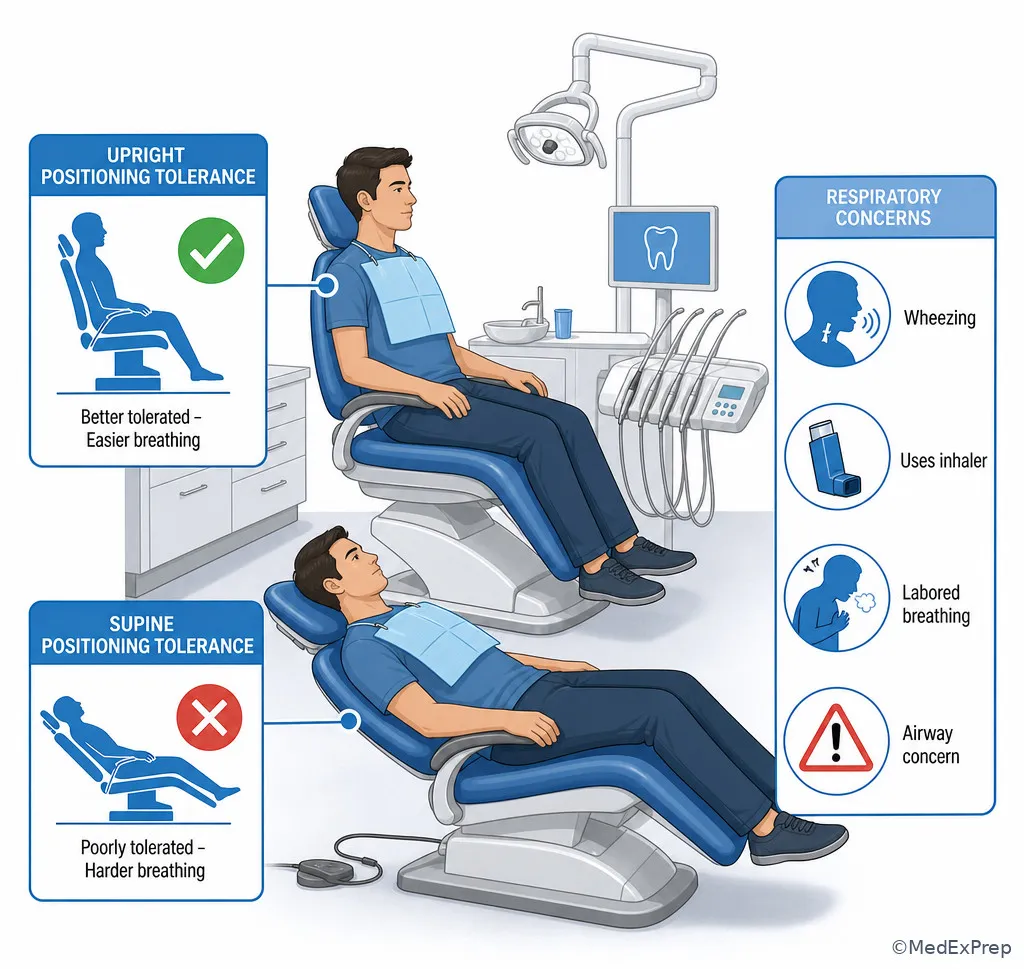
  • Respiratory: active wheezing, shortness of breath, inability to lie back, recent exacerbation.
  • Renal: dialysis schedule, fatigue, bleeding tendency, medication handling.
  • Hepatic: impaired drug metabolism, bruising, bleeding, active liver disease clues.
  • Bleeding disorders: spontaneous bleeding history, easy bruising, prior procedure complications, anticoagulant/antiplatelet use.

WHY THIS IS TESTED: many exam questions hinge on recognizing the single system clue that changes the treatment sequence. The stem may include osteoarthritis, old appendectomy, or seasonal allergies as distractors while the real answer turns on dialysis yesterday or recurrent hypoglycemia this week.

See Fig 2 for a comparison view that compresses the major system-based red flags into a usable mental checklist.

Concept flow: System filter
Sort by organ system
Cardiac, endocrine, respiratory, renal, hepatic, bleeding.

Find the active issue
Look for symptoms, poor control, recent exacerbation, or treatment changes.

Link to dental implication
Bleeding, hypoglycemia, airway tolerance, healing, or medication handling.

Modify or defer
Choose precautions, consultation, or postponement.

Fig 2. System-based risk flag map
Exam takeaway: Match each medical system to the dental hazard it creates so you can spot the one clue that changes care.
flowchart LR
A[Cardiovascular] --> A1[Ischemia or decompensation]
B[Endocrine] --> B1[Hypoglycemia or poor control]
C[Respiratory] --> C1[Airway or positioning intolerance]
D[Renal] --> D1[Bleeding, fatigue, med handling]
E[Hepatic] --> E1[Bleeding, metabolism concerns]
F[Bleeding disorders] --> F1[Procedure hemostasis risk]
A1 --> G[Need to modify, clarify, or defer]
B1 --> G
C1 --> G
D1 --> G
E1 --> G
F1 --> G
Respiratory positioning and airway risk cues
Exam takeaway: Patients who cannot tolerate supine positioning or who have active respiratory distress require reassessment before routine dental care.
Respiratory positioning and airway risk cues

B. Worked example

A 49-year-old woman presents for extraction of a nonrestorable premolar. She has asthma, type 2 diabetes, and a history of easy bruising. She says she has been using her rescue inhaler several times a day since a recent respiratory infection, slept poorly last night because of coughing, and started “a blood thinner” after a leg clot two weeks ago. A distracting detail in the stem is that her previous extraction years ago was uneventful. The task is to choose the most appropriate next step.

Reasoning chain: Identify task: decide whether invasive dental treatment can proceed now. Extract key facts: active respiratory instability after recent infection, frequent rescue inhaler use, recent anticoagulant initiation, planned extraction. Apply rule: multiple active risk flags mean same-day elective extraction is not appropriate until status is clarified and stabilized. Eliminate distractors: proceeding with a shorter appointment is tempting because the tooth is nonrestorable and prior extraction was fine, but current instability matters more than remote history. Referring automatically to an oral surgeon is also tempting because the patient is medically complex, yet the first issue is medical risk clarification, not specialty technical difficulty. Verify: defer extraction, clarify respiratory control and anticoagulant details, and coordinate care as indicated.

C. Exam trap

Common wrong answer: Focus only on the anticoagulant and ignore the worsening asthma. Why it is tempting: extraction questions often trigger a bleeding-only mindset. Single clue that eliminates it: frequent rescue inhaler use after a recent respiratory infection signals active respiratory instability, which alone can make elective treatment inappropriate today.

D. Checkpoint

Question: Which history finding is the strongest reason to delay elective invasive dental treatment pending further assessment?

  1. Well-controlled hypothyroidism managed on a stable long-term dose
  2. Remote appendectomy with no complications
  3. Hospital admission four days ago for worsening heart failure with a medication change yesterday
  4. Seasonal allergic rhinitis controlled with intermittent antihistamine use

Answer: C

  • A: Tempting because endocrine disease can matter; wrong because the clue says well-controlled and stable.
  • B: Tempting because surgery history sounds significant; wrong because it is remote and not related to current instability.
  • C: Correct because recent decompensated heart failure and fresh medication changes indicate unstable disease.
  • D: Tempting because respiratory history can alter dental care; wrong because the condition is mild and controlled here.
If you missed this: Review 1.1.2.2 System-by-system red flags: what changes care and what does not — focus on identifying active instability rather than being distracted by chronic but controlled diagnoses.
Quick Recall:

  • The strongest generic risk flag across systems is recent __________ or recent medication change. Answer: hospitalization/decompensation.
  • True or False: A diagnosis label alone is enough to defer elective dental care. Answer: False.
  • Name the 3 screening questions before routine care. Answer: Active symptoms now, recent changes, and procedure-specific risk.
High-Yield Connection: This concept is tested alongside Vital Signs Interpretation. Know both the history clue and the physiologic clue: a reassuring history can be overturned by abnormal vital signs, and apparently mild abnormal vitals become more concerning when paired with recent hospitalization or active symptoms.
Practitioner Action: ASSESS which organ system is relevant and whether the problem is controlled; INTERVENE by modifying scheduling, positioning, stress reduction, or procedure timing only when disease appears stable; REFER for medical clarification when symptoms are active or the condition has recently changed; DOCUMENT the system involved, the dental implication, and the rationale for any modification or postponement.

1.1.2.3 Recent events that should stop you: hospitalization, infection, medication changes, and procedures

A. Explanation

This section is heavily tested because exam writers can hide major risk inside vague timeline details. The decision conflict is choose same-day care versus reject the urge to “just get started” when the timeline is too fresh. Recent hospitalization, emergency department visits, acute infection, new anticoagulants, steroid bursts, recent dialysis complications, recent cardiac interventions, or recent major medical procedures all suggest the patient’s status may still be evolving. The key rule is not that every recent event mandates deferral; it is that recent unexplained or unresolved change requires clarification before elective care.

WHY THIS IS TESTED: students often ask only “What disease do you have?” instead of “What happened recently?” Timeline questions reveal instability better than problem lists. In OSCE stations, a patient may say, “I was in the ER but it’s nothing,” or “I’m on a new medicine but I don’t remember the name.” That is not a minor detail; it is the reason to pause.

Useful follow-up questions include: Why were you hospitalized? When were you discharged? What changed in your medications? Are you still having symptoms? Did your physician give any restrictions? Have you had fever, antibiotics, or worsening infection recently? See Fig 3 for a decision tree that compresses these timeline triggers.

Concept flow: Recent-change screen
Ask “what changed?”
Hospitalization, infection, new meds, recent procedure, worsening symptoms.

Clarify resolution
Resolved and stable versus unresolved and evolving.

Match to urgency
Urgent dental need may still need temporary management rather than definitive care.

Choose next step
Proceed, modify, defer, consult, or escalate.

Fig 3. Recent-event decision tree
Exam takeaway: Recent hospitalization, new medications, or unresolved infection should trigger timeline clarification before elective treatment.
flowchart TD
A[Recent medical event] --> B{What kind?}
B --> C[Hospitalization or ED visit]
B --> D[New or changed medication]
B --> E[Recent infection or antibiotics]
B --> F[Recent procedure/intervention]
C --> G{Symptoms resolved and status clear?}
D --> G
E --> G
F --> G
G -- No --> H[Defer elective care and clarify]
G -- Yes --> I[Consider modified treatment plan]
H --> J[Consult or refer as indicated]
Fig 4. Medical history timeline interview
Exam takeaway: A focused timeline of hospitalization, infection, and medication changes often reveals the reason to defer elective care.
Fig 4. Medical history timeline interview

B. Worked example

A 35-year-old patient presents for endodontic access on a painful maxillary molar. She has lupus, mild chronic kidney disease, and migraines. She reports a recent urinary infection treated with antibiotics, finished the course two days ago, and says her physician also increased her steroid dose this week because of a flare. She feels “a little shaky,” skipped breakfast, and is asking for definitive treatment today because she has an interview tomorrow. A tempting clue is that the chief complaint is genuinely urgent. The question asks for the best initial management.

Reasoning chain: Identify task: urgent dental pain exists, but you must still screen medical safety. Extract key facts: recent infection, recent steroid increase, skipped breakfast, current shakiness, underlying systemic disease. Apply rule: recent medical change plus current symptoms means the safest approach may be limited urgent stabilization rather than full elective-style definitive care. Eliminate distractors: proceeding with a lengthy definitive procedure is tempting because the tooth hurts and the patient is motivated; however, her current status is not fully clear. Sending her away with no pain management is too passive when a true dental complaint exists. Verify: provide scope-appropriate urgent assessment and limited management as indicated, while clarifying current medical stability and coordinating care if needed.

C. Exam trap

Common wrong answer: Assume that because the dental problem is painful, all medical red flags become secondary. Why it is tempting: urgent dental pain often pressures candidates to favor definitive treatment. Single clue that eliminates it: the patient has recent infection, medication escalation, and current systemic symptoms, making full same-day care potentially unsafe.

D. Checkpoint

Question: A patient scheduled for a routine crown impression says, “I was discharged from the hospital two days ago after pneumonia, and my doctor started two new medications.” He feels better but still becomes short of breath walking from the parking lot. Which is the most appropriate next step?

  1. Proceed because crown impressions are noninvasive and the patient reports improvement.
  2. Defer elective treatment and clarify current recovery status before proceeding.
  3. Proceed only if the patient signs a statement accepting responsibility.
  4. Immediately refer for extraction of the tooth to avoid future visits.

Answer: B

  • A: Tempting because the procedure is noninvasive; wrong because recent hospitalization and persistent exertional dyspnea indicate incomplete recovery.
  • B: Correct because the timeline and residual symptoms make elective care inappropriate until status is clarified.
  • C: Tempting because documentation matters; wrong because consent does not override clinical safety concerns.
  • D: Tempting because fewer visits may seem practical; wrong because changing to a more invasive procedure worsens risk and ignores the medical issue.
If you missed this: Review 1.1.2.3 Recent events that should stop you: hospitalization, infection, medication changes, and procedures — focus on the rule that unresolved recent change requires clarification before elective care.
Practitioner Action: ASSESS the timeline of recent hospital, infection, and medication changes; INTERVENE with limited urgent dental stabilization only when necessary and safe; REFER for medical consultation or urgent medical evaluation if the patient still has active symptoms; DOCUMENT dates, discharge status, patient-reported symptoms, communication with other providers, and your decision-making rationale.

1.1.2.4 Proceed, modify, defer, or refer: choosing the safest defensible next step

A. Explanation

This is the integration step most tested in DLOSCE-style reasoning. The decision conflict is choose a concrete action: proceed routinely, proceed with modifications, defer elective care pending clarification, or escalate urgently. The single finding that resolves the choice is whether there is active instability or unresolved risk that could be worsened by treatment today. Stable patients may need small modifications: shorter visits, morning appointments for diabetes, upright positioning for respiratory comfort, hemostatic planning for bleeding risk, or medication review before invasive care. Patients with unclear or unstable status need a pause, not a heroic workaround.

WHY THIS IS TESTED: exam stems often offer four plausible actions that differ only in timing and scope. One option may be clinically reasonable in another patient but not this one. The best answer is the one that protects safety while staying within entry-level dental scope.

See Fig 5 for a choose-versus-avoid algorithm. Also note the forward connection to the upcoming topics: Vital Signs Interpretation will give you objective physiologic thresholds that can confirm or overturn a history-based plan, and Medication and Allergy Review will sharpen how anticoagulants, steroids, immunosuppressants, and true allergies alter care.

Concept flow: Action selection
Proceed
Condition controlled, no recent changes, low-risk procedure.

Modify
Stable but needs positioning, timing, stress reduction, or hemostatic planning.

Defer
Elective care delayed when status is unclear, unstable, or recently changed.

Refer/Escalate
Emergency symptoms, airway risk, or needs beyond entry-level scope.

Fig 5. Proceed-modify-defer-refer algorithm
Exam takeaway: The best next step depends on whether risk is controlled, unclear, unstable, or emergent.
flowchart TD
A[Medical history reviewed] --> B{Active instability or emergency?}
B -- Yes --> C[Urgent referral / EMS / emergency evaluation]
B -- No --> D{Status unclear or recently changed?}
D -- Yes --> E[Defer elective care and obtain consultation]
D -- No --> F{Stable but requires precautions?}
F -- Yes --> G[Modify appointment and proceed carefully]
F -- No --> H[Proceed routinely]
Dental operatory risk modification checklist
Exam takeaway: Small workflow modifications are appropriate only after you decide the patient is stable enough for outpatient dental care.
Dental operatory risk modification checklist

B. Worked example

A 71-year-old man presents with a broken distal cusp on a mandibular first molar and requests a same-day buildup. He has atrial fibrillation, chronic obstructive pulmonary disease, and chronic hepatitis. He denies chest pain but says he was started on a new anticoagulant five days ago after an emergency visit, becomes winded lying flat, and bruises easily. The distracting clue is that the planned restoration may not seem invasive. The task is to choose the most appropriate next step.

Reasoning chain: Identify task: whether restorative treatment should proceed today. Extract key facts: new anticoagulant, respiratory positioning intolerance, hepatic history with bruising, recent emergency visit. Apply rule: even if the procedure seems modest, the patient’s current medical status is not adequately characterized, and lying-flat intolerance suggests active respiratory limitation. Eliminate distractors: simply repositioning more upright is tempting because it addresses one problem, but it does not resolve the new anticoagulant and recent emergency timeline. Immediate specialist referral is unnecessary if the tooth itself is not beyond general-dentist scope. Verify: defer elective treatment, clarify current medication and stability, and plan care after risk is better defined.

C. Exam trap

Common wrong answer: “Modify and proceed” when the stem actually requires “defer and clarify.” Why it is tempting: candidates know that many chronic diseases need modifications rather than cancellation. Single clue that eliminates it: recent emergency visit plus new medication means the disease status is not yet settled enough to treat as a routine modification case.

D. Checkpoint

Question: Which patient is the best candidate to proceed with planned routine dental care today, using appropriate precautions but without deferral?

  1. A patient with stable type 2 diabetes who ate breakfast, took usual medications, and reports no recent hypoglycemia or medication changes
  2. A patient with chest pressure on exertion this morning who wants a quick filling before work
  3. A patient discharged yesterday after COPD exacerbation who still cannot tolerate lying back
  4. A patient who started a new anticoagulant two days ago and does not know why

Answer: A

  • A: Correct because the disease appears stable and the practical safety questions are satisfactorily answered.
  • B: Tempting because a filling may feel minor; wrong because active ischemic-type symptoms are a red flag.
  • C: Tempting because COPD is common and can be managed with positioning; wrong because the recent exacerbation and ongoing limitation suggest instability.
  • D: Tempting because not all anticoagulant use prohibits care; wrong because the new unexplained medication change requires clarification first.
If you missed this: Review 1.1.2.4 Proceed, modify, defer, or refer: choosing the safest defensible next step — focus on the difference between a stable modification case and an unclear/recently changed case.
Quick Recall:

  • If the stem says “new medication after recent hospitalization,” think __________ before elective care. Answer: clarify/defer.
  • True or False: A minor dental procedure always overrides mild medical uncertainty. Answer: False.
  • Name the four action buckets. Answer: Proceed, modify, defer, refer/escalate.
High-Yield Connection: This concept is tested alongside Medication and Allergy Review and later with Hypertension and Elective Care. Know both the history flag and the medication implication: a new anticoagulant or steroid burst is not just a med list detail; it is evidence of recent clinical change.
Practitioner Action: ASSESS whether the planned procedure is elective, urgent, or emergent and whether the patient appears stable enough for ambulatory care; INTERVENE by proceeding only when status is controlled and precautions are sufficient; REFER for medical consultation, specialist input, or emergency evaluation when risk exceeds entry-level outpatient safety; DOCUMENT your proceed/modify/defer/refer decision and the exact clue that drove it.

1.1.2.5 Communication and documentation: how to defend the safest plan

A. Explanation

In DLOSCE, correct clinical judgment can still be scored down if communication or documentation is weak. The decision conflict is choose vague reassurance versus choose specific, patient-centered explanation with defensible charting. Patients may feel frustrated when treatment is delayed, especially if the dental problem seems obvious. Your task is to explain that the purpose of the pause is safety, not avoidance. The single rule that resolves most communication questions is: state the concern, state the risk, state the next step, and state what to do if symptoms worsen.

WHY THIS IS TESTED: OSCE-style stations evaluate not only recognition of risk but how you respond professionally within scope. You are not acting as the patient’s physician; you are identifying a dental treatment safety issue and coordinating appropriate care.

A strong explanation sounds like this: “Because you were recently hospitalized and your medications changed, I want to make sure your condition is stable before doing elective dental treatment today. The safest next step is to contact your physician or obtain updated information, then reschedule once we know the plan is appropriate.” A strong chart note includes the relevant history details, symptoms denied or endorsed, the reason treatment was deferred or modified, who was contacted, what instructions were given, and follow-up arrangements. See Fig 6 for a practical communication map.

Concept flow: Explain and document
Name the concern
Link the recent medical event to dental safety.

State today’s decision
Proceed with modification, defer, or refer.

Give instructions
What the patient should do next and warning symptoms to watch for.

Document clearly
Record the clue, reasoning, contacts, and follow-up plan.

Fig 6. Patient-centered explanation and chart note elements
Exam takeaway: Safe dental judgment must be paired with clear explanation, consultation planning, and defensible documentation.
Fig 6. Patient-centered explanation and chart note elements
Medical consultation request essentials
Exam takeaway: Consultation requests should ask focused questions about stability, recent changes, and procedural implications rather than sending vague clearance requests.
Medical consultation request essentials

B. Worked example

A 67-year-old woman presents for a bridge impression. She has cirrhosis, atrial fibrillation, and chronic kidney disease. She reports a hospitalization one week ago for “fluid in my belly,” a change in her blood thinner, and easy bruising. She becomes upset when you recommend delay because she took time off work. A tempting but wrong response is to say, “We just need medical clearance,” without further explanation. The better response identifies the risk flag, explains why it changes today’s plan, and outlines next steps.

Reasoning chain: Identify task: communicate a defensible decision. Extract key facts: recent hospitalization, medication change, bruising, elective procedure. Apply rule: explain that treatment is being delayed due to unresolved medical risk, not inconvenience or uncertainty alone. Eliminate distractors: vague reassurance sounds kind but does not convey the actual reason; blaming “policy” undermines professional judgment. Verify: provide clear, respectful explanation, arrange focused consultation, and document the interaction.

C. Exam trap

Common wrong answer: Ask for generic “medical clearance.” Why it is tempting: it sounds official and safe. Single clue that eliminates it: the exam expects a focused question about current stability and treatment implications, not a vague transfer of responsibility.

D. Checkpoint

Question: Which documentation entry is most defensible after deferring elective treatment for a medical history risk flag?

  1. “Treatment canceled. Medical issues.”
  2. “Patient not cleared. Will return later.”
  3. “Recent hospitalization for CHF exacerbation 5 days ago; patient reports new medication adjustments and exertional dyspnea. Elective treatment deferred pending physician clarification of current stability. Patient informed of rationale and instructed to seek urgent medical care if symptoms worsen.”
  4. “No treatment because patient seemed high risk.”

Answer: C

  • A: Tempting because it is brief; wrong because it lacks the specific findings and rationale.
  • B: Tempting because “cleared” is common language; wrong because it does not specify what information is needed or why.
  • C: Correct because it documents the clue, the clinical reasoning, the action, and patient instructions.
  • D: Tempting because it reflects concern; wrong because “seemed high risk” is subjective and not defensible.
If you missed this: Review 1.1.2.5 Communication and documentation: how to defend the safest plan — focus on stating the specific risk flag, the reason for the decision, and the next step.
Practitioner Action: ASSESS the patient’s understanding and concerns about delaying care; INTERVENE with a clear explanation of why the history finding changes today’s plan; REFER by sending a focused consultation question to the appropriate medical provider rather than a vague clearance request; DOCUMENT the exact history finding, clinical decision, informed discussion, and instructions provided.

Exam Traps & Differentiators

Common traps & distractors:

  • Most common wrong answer: proceed with modifications when the stem really requires deferral. Why: many chronic conditions do allow modified care, so candidates overgeneralize. Eliminating clue: recent hospitalization, new meds, or active symptoms.
  • Looks similar but isn’t: stable diabetes versus recent recurrent hypoglycemia. Both have the same diagnosis label; only one is unstable today.
  • Looks similar but isn’t: known anticoagulant use versus a newly started anticoagulant after a recent event. The latter raises a timeline and indication question before care.
  • Looks similar but isn’t: chronic COPD versus current inability to tolerate supine positioning after recent exacerbation. The active limitation is the key clue.
  • Looks similar but isn’t: physician consultation versus generic “clearance.” The exam rewards focused, question-driven consultation.
Pattern in stem Think Do not assume
“Hospitalized last week” Recent instability until proven otherwise That discharge equals readiness for elective dentistry
“Doctor changed my meds yesterday” Status is evolving; clarify why That the change is minor
“I use my inhaler all day lately” Active respiratory instability That upright positioning alone solves the issue
“Started a blood thinner recently” Clarify indication, timing, and planned procedure implications That all dental care must stop or that none is affected
“I feel shaky and skipped breakfast” Consider immediate metabolic risk That a painful tooth makes full treatment automatically appropriate
History clue Stable modification case Deferral/consult case
Diabetes Ate, took meds, no recent episodes Frequent hypoglycemia, symptomatic today, recent regimen changes
Cardiovascular disease No active symptoms, long-term stable regimen Recent admission, exertional symptoms, new meds
Respiratory disease Controlled baseline, no recent exacerbation Recent infection, wheezing, cannot tolerate position
Bleeding risk Known stable plan and procedure-specific precautions Unexplained bruising, new anticoagulant, unclear indication
Renal/hepatic disease Stable follow-up and no recent change Recent decompensation, fatigue, bleeding, medication adjustments

If the stem says...

  • “Recent hospitalization” → think clarify stability before elective care.
  • “Medication changed yesterday” → think the condition may still be unstable.
  • “Short of breath lying back” → think active cardiopulmonary limitation, not just anxiety.
  • “I bruise easily now” → think bleeding risk needs explanation, not assumption.
  • “I finished antibiotics two days ago and still feel unwell” → think recent infection may not be resolved.
  • “I do not know why I was started on this medication” → think do not proceed until the indication is clarified.
Review connection: The traps above test stability-versus-instability judgment. If any felt unfamiliar, revisit 1.1.2.3 Recent events that should stop you: hospitalization, infection, medication changes, and procedures before attempting the Self-check quiz.

Algorithm / Approach

Concept flow: Entry-level dental approach to medical history risk flags
Start with the task
Is today’s care elective, urgent, or emergency-focused?

Screen for red flags
Active symptoms, recent hospitalization, infection, medication changes, bleeding concerns.

Decide stability
Stable and understood → consider proceeding; unclear or unstable → defer/consult; emergency features → escalate.

Match to procedure
Low-risk routine care may proceed with precautions only if the patient is medically stable.

Communicate and document
Explain the reason, next step, warning signs, and follow-up plan.

Outpatient dental risk triage overview
Exam takeaway: Safe outpatient dental decisions begin with identifying whether the patient is stable enough for the setting before choosing the procedure.

Rapid Review

  • Recent hospitalization → treat as possible instability until clarified
  • New medication after acute event → ask why before proceeding
  • Stable chronic disease → usually modify, not automatically defer
  • Active cardiopulmonary symptoms → safety question outranks dental convenience
  • Frequent rescue inhaler use → active respiratory concern, not routine asthma history
  • Skipped meal plus shakiness in diabetes → immediate metabolic risk clue
  • New bruising or unknown blood thinner indication → bleeding risk needs clarification
  • Recent infection with persistent symptoms → unresolved systemic stress
  • Procedure invasiveness matters → but only after patient stability is established
  • Consent does not make unsafe treatment acceptable → safety still governs
  • “Medical clearance” alone → weak unless replaced by focused consultation questions
  • Best chart note → specific clue + reasoning + action + instructions
Memory anchor: For a focused consultation request, use DATE: Diagnosis/current issue, Active symptoms, Timeline of recent change, Exact dental procedure planned.

Self-check quiz

1. A 54-year-old man presents for routine prophylaxis. He has hypertension, hyperlipidemia, and osteoarthritis. He reports no symptoms, no recent hospital visits, and no medication changes for more than a year. Which is the most appropriate next step?

  1. Proceed with routine care using standard history-based precautions
  2. Defer care until a physician provides written clearance
  3. Refer the patient to oral surgery because of multiple diagnoses
  4. Cancel treatment because any cardiovascular history requires deferral

2. A 46-year-old woman presents for a class II restoration. She has type 2 diabetes, hypothyroidism, and chronic low back pain. She ate breakfast, took usual medications, and denies recent hypoglycemia or medication changes. Which finding most strongly supports proceeding with planned care?

  1. Longstanding diagnosis of diabetes
  2. She ate and took usual medications without recent instability
  3. History of back pain that may make lying back uncomfortable
  4. Use of multiple chronic medications

3. A 63-year-old woman presents for extraction of a fractured molar. She has atrial fibrillation, chronic kidney disease, and controlled asthma. She says she was hospitalized five days ago, is unsure why a new medication was started, and bruises more than usual. She feels otherwise well today. Which is the most appropriate next step?

  1. Proceed with the extraction because she currently feels well
  2. Defer the extraction and clarify the recent hospitalization and new medication before treatment
  3. Proceed only if local hemostatic agents are prepared in advance
  4. Refer immediately to the emergency department despite no acute symptoms

4. A 39-year-old patient presents with reversible pulpitis symptoms and requests definitive treatment today. Medical history includes asthma, obesity, and anxiety. The patient reports a recent respiratory infection, increasing rescue inhaler use all week, and difficulty lying fully supine because of shortness of breath. Which finding most requires immediate reconsideration of routine same-day care?

  1. Anxiety about dental treatment
  2. Obesity
  3. Increased rescue inhaler use with positional shortness of breath
  4. Cold sensitivity from the tooth

5. A 58-year-old man presents for a crown seat. He has coronary artery disease, diabetes, and chronic hepatitis. He reports discharge from the hospital three days ago after chest pain evaluation and says his cardiologist adjusted medications yesterday. He insists that the appointment will be quick. Which is the best initial management?

  1. Proceed because crown seating is brief and minimally invasive
  2. Defer elective care and obtain focused medical clarification regarding current stability
  3. Proceed but ask the patient to sign a statement accepting the risk
  4. Switch to extraction because it resolves the tooth issue definitively

6. A 67-year-old woman presents for scaling and root planing. She has diabetes, chronic kidney disease, and heart failure. She denies chest pain. She was hospitalized 10 days ago for fluid overload, says her physician “is still adjusting the medications,” and notes fatigue walking from the parking lot. Which is the most appropriate next step?

  1. Proceed with treatment in shorter segments because she denies chest pain
  2. Proceed after placing the patient more upright and monitoring tolerance
  3. Defer elective periodontal treatment and obtain clarification because heart failure may still be unstable
  4. Refer to a periodontist for all future care because the patient is medically complex

7. A 44-year-old man presents with severe dental pain from a likely symptomatic irreversible pulpitis. He has lupus, a recent steroid dose increase, and completed antibiotics for a skin infection yesterday. Today he skipped breakfast, feels shaky, and asks for full definitive treatment before a long drive. Which is the best next step within entry-level general dentistry scope?

  1. Perform the longest definitive procedure possible because the pain is urgent
  2. Provide limited urgent management after reassessing current systemic status, and defer definitive care if instability persists
  3. Ignore the medical history because the source is clearly odontogenic
  4. Send the patient directly for hospital admission without further assessment

8. A 72-year-old man presents for a routine restoration. He has COPD, atrial fibrillation, and cirrhosis. He denies chest pain but says he started a new blood thinner after an emergency visit four days ago, bruises easily, and becomes short of breath when reclined. Which action is most appropriate?

  1. Proceed in an upright position because the planned procedure is only restorative
  2. Defer treatment and clarify both the recent anticoagulant change and current respiratory tolerance before proceeding
  3. Refer immediately to an oral surgeon for all treatment because he has several systemic diseases
  4. Proceed if the patient states that his physician told him “everything is okay”

Answer key

1. Answer: A

A. Proceed with routine care using standard history-based precautions — Tempting because it may seem too simple when several diagnoses are listed; correct because the scenario specifically gives stable, asymptomatic disease with no recent changes. Single stem clue: no symptoms, no recent hospital visits, no medication changes. Source: ADA guidance on medical history updates and risk assessment supports proceeding when conditions are stable and relevant precautions are addressed.

B. Defer care until a physician provides written clearance — Tempting because cardiovascular history can make candidates overly cautious; incorrect because a generic clearance is not required for every stable chronic condition. Single stem clue: the patient is stable and unchanged for over a year. Source: Little and Falace’s Dental Management of the Medically Compromised Patient.

C. Refer the patient to oral surgery because of multiple diagnoses — Tempting because multiple conditions sound complex; incorrect because the planned care is routine and within general dentistry scope. Single stem clue: routine prophylaxis in a stable outpatient. Source: DLOSCE scope emphasis on safe entry-level management and referral only when necessary.

D. Cancel treatment because any cardiovascular history requires deferral — Tempting because students may remember cardiac red flags without separating stable from unstable disease; incorrect because the diagnosis label alone does not govern the decision. Single stem clue: asymptomatic stable history. Source: ADA Oral Health Topics and medical risk management principles.

If you missed this: Review 1.1.2.1 Foundational screen: stable chronic disease versus unstable disease — focus on the discriminator that stable, asymptomatic, unchanged chronic disease usually allows routine care.

2. Answer: B

A. Longstanding diagnosis of diabetes — Tempting because diabetes is important in dental planning; incorrect because the diagnosis itself does not prove same-day stability. Single stem clue: the question asks what most strongly supports proceeding. Source: ADA diabetes care guidance emphasizes current control and appointment-day readiness.

B. She ate and took usual medications without recent instability — Correct because it directly answers whether the patient is currently prepared for routine outpatient treatment. Single stem clue: ate breakfast, took medications, no recent hypoglycemia or medication changes. Source: ADA and Little/Falace principles for managing diabetes in dental settings.

C. History of back pain that may make lying back uncomfortable — Tempting because it affects positioning; incorrect because it is a modification issue, not the strongest proof of medical stability. Single stem clue: no instability is described from back pain. Source: general patient management positioning principles.

D. Use of multiple chronic medications — Tempting because polypharmacy can signal complexity; incorrect because the safer clue is not the number of medications but the absence of recent changes or instability. Single stem clue: medications are usual and stable. Source: ADA medical history and medication review guidance.

If you missed this: Review 1.1.2.4 Proceed, modify, defer, or refer: choosing the safest defensible next step — focus on the rule that appointment-day stability matters more than the diagnosis label alone.

3. Answer: B

A. Proceed with the extraction because she currently feels well — Tempting because the absence of immediate symptoms can falsely reassure; incorrect because recent hospitalization, unknown new medication, and bruising raise unresolved bleeding and systemic risk questions. Single stem clue: hospitalized five days ago and unsure why a new medication was started. Source: Little/Falace and ADA guidance on clarifying recent medical events before invasive care.

B. Defer the extraction and clarify the recent hospitalization and new medication before treatment — Correct because invasive care should not proceed when key medical history details are unresolved and may change bleeding risk or overall stability. Single stem clue: recent hospitalization plus new unknown medication. Source: ADA Oral Health Topics; DLOSCE patient safety scope.

C. Proceed only if local hemostatic agents are prepared in advance — Tempting because bruising suggests bleeding risk and hemostatics are useful; incorrect because preparation does not replace understanding why the patient was recently hospitalized or what the new drug is. Single stem clue: the medication indication is unknown. Source: ADA anticoagulant guidance and risk-assessment principles.

D. Refer immediately to the emergency department despite no acute symptoms — Tempting because hospitalization sounds serious; incorrect because there is no sign of current emergency instability. The need is clarification, not automatic ED transfer. Single stem clue: she feels well today and no acute emergency features are given. Source: entry-level dental triage standards.

If you missed this: Review 1.1.2.3 Recent events that should stop you: hospitalization, infection, medication changes, and procedures — focus on the discriminator that unknown recent change makes invasive care unsafe to proceed.

4. Answer: C

A. Anxiety about dental treatment — Tempting because anxiety can complicate appointments; incorrect because anxiety alone does not explain worsening respiratory symptoms. Single stem clue: increased rescue inhaler use and positional shortness of breath point to active respiratory disease. Source: respiratory risk management principles in dental settings.

B. Obesity — Tempting because obesity can affect positioning and airway concerns; incorrect because the more immediate and actionable clue is active worsening asthma control. Single stem clue: all week increasing inhaler use after recent infection. Source: Little/Falace respiratory disease guidance.

C. Increased rescue inhaler use with positional shortness of breath — Correct because it signals active respiratory instability, not simply a chronic diagnosis. Single stem clue: inability to lie fully supine because of dyspnea. Source: ADA and standard outpatient dental medical-risk guidance.

D. Cold sensitivity from the tooth — Tempting because it explains the dental complaint; incorrect because it does not determine medical safety. Single stem clue: the question asks what requires reconsideration of routine care. Source: DLOSCE emphasis on prioritizing safety over definitive care.

If you missed this: Review 1.1.2.2 System-by-system red flags: what changes care and what does not — focus on the respiratory discriminator of worsening control and positional intolerance.

5. Answer: B

A. Proceed because crown seating is brief and minimally invasive — Tempting because the procedure itself seems minor; incorrect because recent chest-pain hospitalization and medication adjustment suggest unresolved cardiovascular instability. Single stem clue: discharged three days ago after chest pain evaluation. Source: Little/Falace cardiovascular risk guidance.

B. Defer elective care and obtain focused medical clarification regarding current stability — Correct because the dental procedure is elective and the recent event directly raises safety concerns. Single stem clue: cardiologist adjusted medications yesterday. Source: ADA medical risk management principles.

C. Proceed but ask the patient to sign a statement accepting the risk — Tempting because documentation and autonomy matter; incorrect because informed consent does not legitimize unsafe elective treatment. Single stem clue: unresolved recent cardiac evaluation. Source: ethical standards for informed consent and standard of care.

D. Switch to extraction because it resolves the tooth issue definitively — Tempting because one visit may seem efficient; incorrect because it is more invasive and does not address the medical issue. Single stem clue: the problem is medical stability, not prosthodontic planning. Source: treatment sequencing principles in medically compromised patients.

If you missed this: Review 1.1.2.4 Proceed, modify, defer, or refer: choosing the safest defensible next step — focus on the discriminator that even low-invasiveness elective procedures should be deferred when recent cardiovascular instability is unresolved.

6. Answer: C

A. Proceed with treatment in shorter segments because she denies chest pain — Tempting because shorter visits are often useful modifications; incorrect because denial of chest pain does not rule out unstable heart failure. Single stem clue: recent hospitalization for fluid overload with ongoing medication adjustments. Source: Little/Falace and outpatient dental cardiovascular management principles.

B. Proceed after placing the patient more upright and monitoring tolerance — Tempting because positioning addresses some cardiopulmonary symptoms; incorrect because it treats only comfort while ignoring likely unresolved instability. Single stem clue: fatigue walking from the parking lot suggests ongoing poor functional tolerance. Source: cardiovascular risk assessment standards.

C. Defer elective periodontal treatment and obtain clarification because heart failure may still be unstable — Correct because recent decompensation plus medication adjustment signals that the patient may not yet be stable for elective care. Single stem clue: “physician is still adjusting the medications.” Source: ADA and Little/Falace medical management guidance.

D. Refer to a periodontist for all future care because the patient is medically complex — Tempting because complexity can suggest referral; incorrect because the key issue is medical stability, not specialty-level periodontal scope. Single stem clue: scaling and root planing remains within general dentistry once medically appropriate. Source: DLOSCE scope guardrails.

If you missed this: Review 1.1.2.1 Foundational screen: stable chronic disease versus unstable disease — focus on the discriminator that heart failure can be unstable even without chest pain when recent decompensation and poor exertional tolerance are present.

7. Answer: B

A. Perform the longest definitive procedure possible because the pain is urgent — Tempting because the dental complaint is real and severe; incorrect because recent infection, steroid escalation, skipped breakfast, and shakiness raise current medical concerns that may make a long definitive visit unsafe. Single stem clue: shaky after skipping breakfast with recent systemic changes. Source: dental urgent care and medical risk management principles.

B. Provide limited urgent management after reassessing current systemic status, and defer definitive care if instability persists — Correct because it balances the urgent dental complaint with patient safety and remains within entry-level scope. Single stem clue: urgent pain exists, but the patient also has signs of possible current metabolic or systemic instability. Source: ADA urgent care guidance and general dental scope expectations.

C. Ignore the medical history because the source is clearly odontogenic — Tempting because the tooth diagnosis appears straightforward; incorrect because a correct dental diagnosis does not cancel medical risk screening. Single stem clue: recent steroid increase and current shakiness. Source: DLOSCE patient safety emphasis.

D. Send the patient directly for hospital admission without further assessment — Tempting because the case sounds complex; incorrect because hospital admission is beyond the dentist’s role here and the stem does not provide clear emergency features requiring immediate hospital-level escalation. Single stem clue: no airway compromise, altered mental status, or similar emergency findings are described. Source: scope-of-practice limits and emergency triage standards.

If you missed this: Review 1.1.2.3 Recent events that should stop you: hospitalization, infection, medication changes, and procedures — focus on the discriminator that urgent dental pain may call for limited stabilization rather than full definitive care when current systemic status is uncertain.

8. Answer: B

A. Proceed in an upright position because the planned procedure is only restorative — Tempting because upright positioning can reduce respiratory discomfort and a restoration may seem low risk; incorrect because new anticoagulant use after a recent emergency visit and recline intolerance indicate unresolved issues beyond simple positioning. Single stem clue: new blood thinner started four days ago after an emergency visit. Source: medical risk management and anticoagulant review principles.

B. Defer treatment and clarify both the recent anticoagulant change and current respiratory tolerance before proceeding — Correct because two active red flags are present: recent medication change and current positional dyspnea. Single stem clue: shortness of breath when reclined plus new anticoagulant with unclear recent indication. Source: ADA guidance; Little/Falace.

C. Refer immediately to an oral surgeon for all treatment because he has several systemic diseases — Tempting because specialist referral can feel safer; incorrect because the issue is not specialist dental technique but unresolved medical status. Single stem clue: routine restoration remains within general dentist scope once medically appropriate. Source: DLOSCE scope guardrails.

D. Proceed if the patient states that his physician told him “everything is okay” — Tempting because verbal reassurance from a physician sounds sufficient; incorrect because vague secondhand reassurance does not substitute for clarifying what changed and whether current symptoms are compatible with safe care. Single stem clue: current recline intolerance remains unresolved. Source: focused consultation and documentation standards.

If you missed this: Review 1.1.2.2 System-by-system red flags: what changes care and what does not and 1.1.2.4 Proceed, modify, defer, or refer: choosing the safest defensible next step — focus on the discriminator that multiple active red flags override the apparently minor nature of the planned restoration.

References

  • Little, James W., et al. Dental Management of the Medically Compromised Patient. 9th ed., Elsevier, 2018.
  • American Dental Association. “Medical History and Dental Treatment Considerations.” ADA Oral Health Topics, American Dental Association.
  • American Dental Association. “Oral Anticoagulant and Antiplatelet Medications and Dental Procedures.” ADA Oral Health Topics, American Dental Association.
  • American Diabetes Association. Standards of Care in Diabetes. American Diabetes Association, current edition.
  • Greenberg, Martin S., and Michael Glick, editors. Burket’s Oral Medicine. 13th ed., PMPH USA, 2021.

Last reviewed: May 14, 2026

Keep reading, free

Enter your email to read lesson 2 now.

Free. We may also email you about our programs. No spam, and you can ask us to remove your email at any time.

Liked it?

DLOSCE Prep Course (DLOSCE) has 81 lessons.

DLOSCEPrep
Programs
For organizations
ContactLog inGet a free guide